Happy nurses week! In honor of this special occasion, I'm blogging for the first time in months...And it will be a nurse story. Because it's nurses week. And because I keep wanting to tell this story to every person I encounter, and I'm quite certain they will get sick of the retelling.
Or be shocked at my crassness.
But the crassness is what makes it so great!
Tuesday I went in to say hello and do an assessment on a 66 year old gentleman who was in mental status change. He had suffered from a stroke, and he did not have any residual effects physically, but as he told me over and over, "My head is messed up." Whether it is due to his stroke, history of drug abuse, or seizures, I'm not sure. But he was confused. He would get an idea in his head, and he would say it over and over and over. For example, he had wanted me to call his son to go check on his wife at the nursing home, only he couldn't remember the number. I looked it up in the computer, but before I got a chance to help him with the call (any activity with this gentleman took a good amount of time due to his mental processing deficit), he remembered the number.
867-5309! 867-5309! 867-5309!
He shouted it out from his room so LOUDLY that I could hear it clearly in my patient's room two doors down. And, fortunately he had learned to use the call button...
"May I help you," asked the unit secretary.
"867-5309! 867-5309! 867-5309!"
Okay, that's not the real number he gave. He gave the correct number, which I memorized due to him hollering it for a good 20 minutes straight, but I cannot give it to you, lest you call his son and harass him. Besides, 867-5309 will be stuck in your head all day. You're welcome.
Anyway, all of that drawn out background was to get a base of his mentation for you.
I was charting his assessment in the computer. "I have to pee!"
"Okay, go ahead and go. The bathroom is right there." I indicated the door, and knew full well he could get up and walk, as he'd been wandering the hall all night long, and had in fact gotten himself tied up for not staying in his room, and wandering into other patient's rooms...
"I gotta pee!"
"Okay..." And I repeated the instructions as I continued to chart....And I repeated. And repeated.
And repeated.
After I had completed the charting, I turned to him and said, "Alright, let's get you up to the bathroom." And thus began a 10 minute step by step instruction session to get this six foot man out of bed and to the bathroom, where he walked to the toilet....and stood.
"Lift your gown up so you can pee."
"Okay." And he did.
"Alright, you might want to pull down your diaper."
"Okay." Nothing....I said again, "You need to pull down your diaper."
"Okay." Still standing with his gown wadded up in his hands.
And with a mental shrug I undid his diaper and pulled it off. "Alright. You can pee now."
And he proceeded to pee all over the floor. "Sir, you need to grab hold of that thing and take about two steps forward. You are missing the toilet." Now, some of you may be shocked at my bluntness, but sometimes I wish I had that gumption when I was 16 working at our local gas station and cleaning pee up daily after specific men came in for their morning coffee and gossip session.
Anyway, he said, "Oh my! Oh no! I peed all over my nuts! This is TERRIBLE! And the floor! How TERRIBLE! TERRIBLE! TERRIBLE!"
"It's okay. Just step closer, and aim a little better." And he did. But he continued to rant, "I peed on my nuts! You will have to wash my nuts! It's awful!"
I got a warm washcloth, waited for him to finish, and when he said, "Well, that ain't much, but that's all I can do these days," I handed him the rag and said, now clean yourself up. Which he thankfully began to do, WITHOUT step by step direction.
"This is terrible. You are washing my nuts! You don't get paid enough to wash my nuts! Oh no. I'm so sorry I peed all over my nuts and you have to wash them."
"It's okay, sir. You are washing them, not me."
Yet he continued to dutifully scrub and apologize..."I'm so sorry I peed on my nuts! You have to wash my nuts! It's terrible!
At last I deemed that they were certainly clean. "Alright, that's good. Now throw the washcloth in this bag, and wash your hands."
So he did, and continued to say, "I peed on my nuts! I'm so sorry! Now you have to wash them! You don't get paid enough to wash nuts!"
At last I convinced him that he could stop washing his hands and to return to bed. Of course, all the way to bed he chanted in a loud voice, "You have to wash my nuts! I peed all over my nuts! This is TERRIBLE!"
And I continued to say "It's okay," and "You already cleaned your nuts, now let's get a diaper back on and get you back in bed" all the while fighting to not burst into laughter lest I hurt his feelings. Because, rest assured Gentle Reader, men do NOT enjoy laughter that involves their nuts. Life experience as a nurse, I promise this is fact.
After spending five minutes convincing him to get in bed, I finally was able to leave the room with him apologizing all of the way out the door....
"I peed on my nuts! This is TERRIBLE! You have to wash my nuts! I'm so sorry! You don't get paid enough to wash my nuts!"
And I stepped out in the hall and around the corner of his door. And collapsed against the wall shaking with silent laughter.
Happy nurses week!
Showing posts with label nursing. Show all posts
Showing posts with label nursing. Show all posts
Friday, May 17, 2013


Friday, February 17, 2012
One Month Older
Monday I stayed late to sedate a patient who needed a cerebral angiogram. That's a big term for a study of the vessels in the brain. I dread these cases.
Mostly because brains freak me out, and I've never been that comfortable with what to do with tubes and bolts sticking out the top of people's heads....
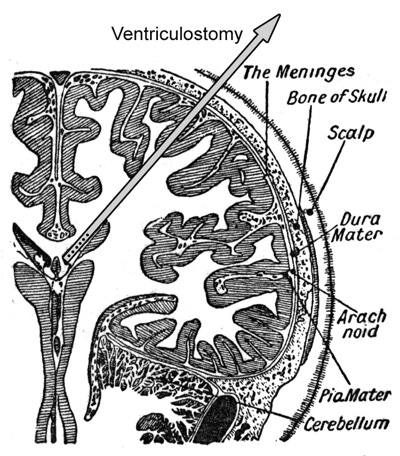
Here is a picture to tell you where the drain sits inside the brain:
The external collections system of the brain is set to only drain if the pressure within the brain gets above a certain point. The drainage system has to stay level with the ear canal to monitor this pressure accurately. Our doctors have to move the procedure table up and down and back and forth all through the case. This means that not only are we giving medications, monitoring heart rate, blood pressure, oxygen, etc. Now we are freaking out on a drain that is vital to helping decrease injury to the brain. My shoulders are turning to earrings just thinking about this...
However, regardless of my wants and fears, my hospital has hired two new neuro surgeons, and signed a contract for two neuro interventional radiologists to work in our department...A neuro interventionalist puts a catheter in the femoral artery and threads it up to the brain to do interventions...Mostly put coils into vessels that are bleeding. Do you know the sort of confidence they must have to carry to put coils in a brain through a catheter that originates at the groin?
Ack.
The other thing that is stressing my fellow coworkers and me out is that while we have all been reading up on and taking skills tests on these neuro patients, we haven't had much real life experience. It's kind of like when you graduate nursing school and you have lots of head knowledge but can't put it all together easily. Only instead of working with a preceptor, we are wading through the trenches on call cases at night. Thus far we've learned that most patients don't tend to have crises in normal business hours. If the patient is in the ICU we can drag that nurse along with us, but if the patient is still in the ER, we are on our own. We've actually started adding a second call nurse to come in as a back up if the case is really hairy. We are all super excited about more call.
Not.
Anyway, Monday night as my shift was ending I found out we had an intracranial hemorrhage in the ER. "Don't panic, Dr. G is going to do it, and it's just diagnostic." That was good news for me as Dr. G is "my" doctor and he works much faster than the neuro interventionalists. Plus, I know him better (and he knows me) so we work better together. For instance, he understands that I'm going to get snappy and possibly tell him to "be quiet and let me catch up" with these urgent cases where everyone is rush rush rushing and I haven't even had time to give the patient medications, or if I have I haven't charted a single thing I've done, or "you are making me nervous positioning that table. I don't have my lead on yet." And he knows I don't want to get fried, so he would never xray while I am "naked." But again, these are all things I tend to get snippy about in these late cases. Especially considering I was hungry...
You have to understand that when an emergent case occurs during the day, even though I may be the only nurse in the room, there are at least three other nurses just outside my door. At night, I'm the only nurse unless the patient is from the ICU, and then I can drag that nurse along with me to the procedure. When things are going down, it's always best to have a pack mentality. You know, safety in numbers. The more people that I have in the room with me that meet my skill set, the better I feel...
I was surprised when I went to get the patient from the ER to see that she is only one month older than me. She has six children, the youngest of which is just a baby. She was actually alert and oriented, but she had "the worst headache of her life." She was walking into the grocery store that morning and her headache, which she'd had for three days, became so bad that she felt as if something exploded in her head. She called 911 and ended up with me that night. After chatting with her I learned that she had went to her doctor after she had her baby, and the doctor said her blood pressure was normal so she quit taking her medicine. She didn't understand that the blood pressure was normal BECAUSE she was on medicine.
Sometimes I get so frustrated with the ignorance of people. It all seems so pointless and at times just plain stupid. However, I also realize that a big piece of it is lack of proper education.
And the jaded nurse in me also realizes that another big piece is noncompliance. Unfortunately I see a lot more noncompliance than lack of education. Truthfully I think this was really a lack of understanding.
She was a never smoker, denied any drug use, occasional drinker with the brain of a 70 year old.
High blood pressure: The silent killer.
After the procedure was over her daughter had arrived. She looked about the age of my girls.
And she was scared to death. I pulled her mom's oxygen tubing off of her face and took her surgical hat that I had covering her hair off and encouraged the girl to chat with her mom to see that she was okay...She was being so good and so strong and trying so hard to hold the big pools of tears in her eyes back. Her voice was wobbly and her breath was shuddering.
For some dumb reason, I said "Baby it's okay. Your mommy is going to be okay. I promise."
No sooner did those words leave my mouth than I wanted to take them back. I can't make that promise! I've never made such a dumb promise in my life! I let my emotions get the best of me, and I made a rash statement.
Those words haunted me off and on throughout Monday night.
The next day we had to repeat part of the study to get a little clearer picture of one portion of her brain. Her daughter was not with her, but I learned that the little girl had spent the night at the hospital and was home resting. By the time we were complete with the follow up study, her daughter was back at the hospital. She rushed up and gave her mommy a kiss on the cheek after I quickly whipped as many tubes off of her mommy that I safely could.
I am not sure what the decision was based on our follow up films. I had read in the neuro surgeon's note that was written before our study that he was "asking for a repeat, with probable surgery in the morning." I didn't get to learn what the findings were because as soon as I returned to our department I had to tend to another patient who was having irregular heart beats. Then I had another patient in the ER that we had to go get and do a procedure on...
And then it was 7pm, and I had never even eaten lunch, so I simply clocked out and came home.
But my little momma has been on my mind. I pray that she's okay so that she can be a mommy to her six children.
P.S. I originally typed this post on Wednesday. On Thursday I went to check on her. She had gone through surgery to clip the aneurysm in her brain on Wednesday well. On Thursday she was alert and oriented and doing great. Hopefully she will have a full recovery.
Mostly because brains freak me out, and I've never been that comfortable with what to do with tubes and bolts sticking out the top of people's heads....
Here is a picture to tell you where the drain sits inside the brain:
 |
| source |
The external collections system of the brain is set to only drain if the pressure within the brain gets above a certain point. The drainage system has to stay level with the ear canal to monitor this pressure accurately. Our doctors have to move the procedure table up and down and back and forth all through the case. This means that not only are we giving medications, monitoring heart rate, blood pressure, oxygen, etc. Now we are freaking out on a drain that is vital to helping decrease injury to the brain. My shoulders are turning to earrings just thinking about this...
However, regardless of my wants and fears, my hospital has hired two new neuro surgeons, and signed a contract for two neuro interventional radiologists to work in our department...A neuro interventionalist puts a catheter in the femoral artery and threads it up to the brain to do interventions...Mostly put coils into vessels that are bleeding. Do you know the sort of confidence they must have to carry to put coils in a brain through a catheter that originates at the groin?
Ack.
The other thing that is stressing my fellow coworkers and me out is that while we have all been reading up on and taking skills tests on these neuro patients, we haven't had much real life experience. It's kind of like when you graduate nursing school and you have lots of head knowledge but can't put it all together easily. Only instead of working with a preceptor, we are wading through the trenches on call cases at night. Thus far we've learned that most patients don't tend to have crises in normal business hours. If the patient is in the ICU we can drag that nurse along with us, but if the patient is still in the ER, we are on our own. We've actually started adding a second call nurse to come in as a back up if the case is really hairy. We are all super excited about more call.
Not.
Anyway, Monday night as my shift was ending I found out we had an intracranial hemorrhage in the ER. "Don't panic, Dr. G is going to do it, and it's just diagnostic." That was good news for me as Dr. G is "my" doctor and he works much faster than the neuro interventionalists. Plus, I know him better (and he knows me) so we work better together. For instance, he understands that I'm going to get snappy and possibly tell him to "be quiet and let me catch up" with these urgent cases where everyone is rush rush rushing and I haven't even had time to give the patient medications, or if I have I haven't charted a single thing I've done, or "you are making me nervous positioning that table. I don't have my lead on yet." And he knows I don't want to get fried, so he would never xray while I am "naked." But again, these are all things I tend to get snippy about in these late cases. Especially considering I was hungry...
You have to understand that when an emergent case occurs during the day, even though I may be the only nurse in the room, there are at least three other nurses just outside my door. At night, I'm the only nurse unless the patient is from the ICU, and then I can drag that nurse along with me to the procedure. When things are going down, it's always best to have a pack mentality. You know, safety in numbers. The more people that I have in the room with me that meet my skill set, the better I feel...
I was surprised when I went to get the patient from the ER to see that she is only one month older than me. She has six children, the youngest of which is just a baby. She was actually alert and oriented, but she had "the worst headache of her life." She was walking into the grocery store that morning and her headache, which she'd had for three days, became so bad that she felt as if something exploded in her head. She called 911 and ended up with me that night. After chatting with her I learned that she had went to her doctor after she had her baby, and the doctor said her blood pressure was normal so she quit taking her medicine. She didn't understand that the blood pressure was normal BECAUSE she was on medicine.
Sometimes I get so frustrated with the ignorance of people. It all seems so pointless and at times just plain stupid. However, I also realize that a big piece of it is lack of proper education.
And the jaded nurse in me also realizes that another big piece is noncompliance. Unfortunately I see a lot more noncompliance than lack of education. Truthfully I think this was really a lack of understanding.
She was a never smoker, denied any drug use, occasional drinker with the brain of a 70 year old.
High blood pressure: The silent killer.
After the procedure was over her daughter had arrived. She looked about the age of my girls.
And she was scared to death. I pulled her mom's oxygen tubing off of her face and took her surgical hat that I had covering her hair off and encouraged the girl to chat with her mom to see that she was okay...She was being so good and so strong and trying so hard to hold the big pools of tears in her eyes back. Her voice was wobbly and her breath was shuddering.
For some dumb reason, I said "Baby it's okay. Your mommy is going to be okay. I promise."
No sooner did those words leave my mouth than I wanted to take them back. I can't make that promise! I've never made such a dumb promise in my life! I let my emotions get the best of me, and I made a rash statement.
Those words haunted me off and on throughout Monday night.
The next day we had to repeat part of the study to get a little clearer picture of one portion of her brain. Her daughter was not with her, but I learned that the little girl had spent the night at the hospital and was home resting. By the time we were complete with the follow up study, her daughter was back at the hospital. She rushed up and gave her mommy a kiss on the cheek after I quickly whipped as many tubes off of her mommy that I safely could.
I am not sure what the decision was based on our follow up films. I had read in the neuro surgeon's note that was written before our study that he was "asking for a repeat, with probable surgery in the morning." I didn't get to learn what the findings were because as soon as I returned to our department I had to tend to another patient who was having irregular heart beats. Then I had another patient in the ER that we had to go get and do a procedure on...
And then it was 7pm, and I had never even eaten lunch, so I simply clocked out and came home.
But my little momma has been on my mind. I pray that she's okay so that she can be a mommy to her six children.
P.S. I originally typed this post on Wednesday. On Thursday I went to check on her. She had gone through surgery to clip the aneurysm in her brain on Wednesday well. On Thursday she was alert and oriented and doing great. Hopefully she will have a full recovery.
Sunday, February 12, 2012
What EXACTLY is She Trying to Tell Me?
A while back we had some friends over for dinner. I don't remember exactly what we were talking about, but I do know we somehow got on the discussion of scary girls in high school. All of the scary girls in my high school had this strange habit of cutting their hair extremely short from the top of their ears down, but leaving the rest of it long. You wouldn't really notice it until they pulled it up in a pony tail. I never understood it, but I always thought it strange...
I guess I should qualify the above statement about scary girls. Two scary girls (who were sisters) in my school had that hair cut. Some other girls did too. They weren't scary at all. However, because the two scary sisters had that hair, I've always associated it with the thought that the gal sporting that 'do may take it into her head to drag me into the parking lot by my hair and pound on me at any given point in time...However, THAT story is a post for another day. Today's post is about something else, not high school bullies....
So. My friend Tammy and I were discussing that hair cut. And how we were scared of girls with that hair...Okay I was scared of girls with that hair.
The next Monday I went to work and had a lady about my age as a patient. She was having a biopsy done of a mass on her lung. As I began to get her ready for her procedure, I noticed that she had what I fondly refer to as "prison tats." You know those tattoos that are that navy blue color and poorly delineated? A lot of the people who have those received them from friends in their garages before tattoo parlors were legal in Oklahoma....Or they received them in exchange for smokes in jail...
I seldom ask where they obtained them. As a matter of fact, I actually refrain from inquiring after them at all, because I really just DON"T want to know.
Anyway, I had a lady my age. She had prison tats...
And she had bad teeth. She was really kind of pretty in a rough sort of way. I couldn't help but silently think that it was a shame she saw fit to put poorly designed tattoos on her inner wrist and chest...
And I thought it was too bad that she apparently had a history of methamphetamine abuse, or her mother had taken tetracycline when she was pregnant, or in her early stage of her childhood causing her to have become discolored. I really doubted the antibiotic theory as I don't think it affects adult teeth...
Do you find it strange that nurses are taking in so many details and trying to guess causes as we are chatting and starting IVs and whatnot? I don't do it consciously. It just happens.
I continued my care of her and learned that she was a smoker. Well, actually I was pretty sure she was a smoker the minute I listened to her lungs, and sooner than that, when I put her coat in the closet and smelled the smoke...
Anyway, she asked if she could go have a smoke before her procedure. I said I didn't think so, and that since she came right out and mentioned it, I was now compelled to give her my "quit smoking lecture."
Her friend was also lecturing her on quitting Diet Coke. I said I wasn't quite as concerned with her soft drink habit as I was the smoking...
Anyway, eventually as I took her back to the table and began to hook her up to my monitors, I learned that she was a prison guard.
?
She was a tiny little thing.
Anyway, that surprised me.
It took a ridiculous amount of medicine to get her sedated. She had been taking pain pills and anxiety pills, so her tolerance to medications was pretty high...At one point I asked her if she was doing okay. she said she was fine but not at all sleepy. I told her that I wasn't certain I'd be able to get her to sleep, but if she wasn't scared, I was calling it good. She tolerated the procedure well.
After her procedure, when I had her back in her bay, I noticed as she pulled up her hair that short under the long layer hair cut...And I mentally checked off, "prison tats, bad teeth, scary girl haircut, and now I learn she's a prison guard." Yep. She pretty much met all of my stereotypes.
It's hard not to become judgmental in my world. You hear so many stories, and see the same consequence to the same action over and over so that it gets hard to not look at people and go, "What are you thinking?"
Anyway, she had to stick around a while, which led to some chatting as she was my last patient to go home for the day. She asked why I couldn't get her to sleep. "Well, unfortunately you've been using a lot of medications at home that act the same brain receptors as my sedation medications. That means you are resistant to them, and I would have ended up giving you enough to dart an elephant to get you to sleep. I decided that rather than that, we would just shoot for super relaxed."
She agreed that she had felt fine and didn't really mind the procedure at all.
However, she did ask if I'd ever thought of working in the prison system. She thought I'd make a "great prison nurse."
What exactly does that mean?
I decided I didn't want to know. Perhaps I've become a bit TOO matter of fact in my job?
Something to think about.
I guess I should qualify the above statement about scary girls. Two scary girls (who were sisters) in my school had that hair cut. Some other girls did too. They weren't scary at all. However, because the two scary sisters had that hair, I've always associated it with the thought that the gal sporting that 'do may take it into her head to drag me into the parking lot by my hair and pound on me at any given point in time...However, THAT story is a post for another day. Today's post is about something else, not high school bullies....
So. My friend Tammy and I were discussing that hair cut. And how we were scared of girls with that hair...Okay I was scared of girls with that hair.
The next Monday I went to work and had a lady about my age as a patient. She was having a biopsy done of a mass on her lung. As I began to get her ready for her procedure, I noticed that she had what I fondly refer to as "prison tats." You know those tattoos that are that navy blue color and poorly delineated? A lot of the people who have those received them from friends in their garages before tattoo parlors were legal in Oklahoma....Or they received them in exchange for smokes in jail...
I seldom ask where they obtained them. As a matter of fact, I actually refrain from inquiring after them at all, because I really just DON"T want to know.
Anyway, I had a lady my age. She had prison tats...
And she had bad teeth. She was really kind of pretty in a rough sort of way. I couldn't help but silently think that it was a shame she saw fit to put poorly designed tattoos on her inner wrist and chest...
And I thought it was too bad that she apparently had a history of methamphetamine abuse, or her mother had taken tetracycline when she was pregnant, or in her early stage of her childhood causing her to have become discolored. I really doubted the antibiotic theory as I don't think it affects adult teeth...
Do you find it strange that nurses are taking in so many details and trying to guess causes as we are chatting and starting IVs and whatnot? I don't do it consciously. It just happens.
I continued my care of her and learned that she was a smoker. Well, actually I was pretty sure she was a smoker the minute I listened to her lungs, and sooner than that, when I put her coat in the closet and smelled the smoke...
Anyway, she asked if she could go have a smoke before her procedure. I said I didn't think so, and that since she came right out and mentioned it, I was now compelled to give her my "quit smoking lecture."
Her friend was also lecturing her on quitting Diet Coke. I said I wasn't quite as concerned with her soft drink habit as I was the smoking...
Anyway, eventually as I took her back to the table and began to hook her up to my monitors, I learned that she was a prison guard.
?
She was a tiny little thing.
Anyway, that surprised me.
It took a ridiculous amount of medicine to get her sedated. She had been taking pain pills and anxiety pills, so her tolerance to medications was pretty high...At one point I asked her if she was doing okay. she said she was fine but not at all sleepy. I told her that I wasn't certain I'd be able to get her to sleep, but if she wasn't scared, I was calling it good. She tolerated the procedure well.
After her procedure, when I had her back in her bay, I noticed as she pulled up her hair that short under the long layer hair cut...And I mentally checked off, "prison tats, bad teeth, scary girl haircut, and now I learn she's a prison guard." Yep. She pretty much met all of my stereotypes.
It's hard not to become judgmental in my world. You hear so many stories, and see the same consequence to the same action over and over so that it gets hard to not look at people and go, "What are you thinking?"
Anyway, she had to stick around a while, which led to some chatting as she was my last patient to go home for the day. She asked why I couldn't get her to sleep. "Well, unfortunately you've been using a lot of medications at home that act the same brain receptors as my sedation medications. That means you are resistant to them, and I would have ended up giving you enough to dart an elephant to get you to sleep. I decided that rather than that, we would just shoot for super relaxed."
She agreed that she had felt fine and didn't really mind the procedure at all.
However, she did ask if I'd ever thought of working in the prison system. She thought I'd make a "great prison nurse."
What exactly does that mean?
I decided I didn't want to know. Perhaps I've become a bit TOO matter of fact in my job?
Something to think about.
Saturday, January 28, 2012
The Story of My Tattoo
It seems as if EVERYONE wants or has a tattoo these days.
I got my first tattoo in 1993. I was a Junior in high school.
And it wasn't real.
You see, it was a very classy rub on tattoo. I think I got it from Claire's. I loved it. I proudly sported it on my ankle, just above my bobby sock during basketball season so everyone could admire it's beauty in my cheerleading uniform.
The thing about rub on tattoos is they come off. So a few days later I put a butterfly tattoo on my OTHER ankle. It was sooooo beautiful. I think it was a big blue butterfly. But I could be mistaken.
"Do you know what people think of you when they see those tattoos on your legs?" my mom would ask.
"They think it's in a different location every time they see it," was my smart reply. (I fear I frequently needed my face smacked in high school.)
So in high school I had a love affair with tattoos. I would put them on my shoulders if I knew I was going to wear a sleeveless shirt, but I quickly learned they weren't as pretty as the ones I put on my legs, due to my resistance to shaving my arms...
In those days tattoo parlors were illegal in Oklahoma. I turned 18 in 1993, and I think my parents were quite relieved that I could not just wander up the street and get a REAL tattoo. However, I was determined that one day I would have a tattoo. I hadn't settled on the exact design, or even location. You see, NOBODY had tattoos in those days. Well, unless you were a biker, active military, or a veteran. But other than that, no all American girls had tattoos. However, for some reason I had determined it was my destiny to decorate my body with colored ink.
I graduated high school in 1994. That May I went to work at a regional hospital in our area as a nurse's aide. I did all of those things that nurses receive such glory for. You know: Bed baths, toileting, diaper changing, spoon feeding, and lets not forget overall cleaner of vomit. I always tell people who are considering nursing as a profession to work as an aide before they do it. If you can do the most menial part of the job and still love it, then it is definitely your calling.
So there I was 18 years old, working as a nurse's aide and pondering the exact location of my permanent tattoo, and how I was going to manage to get said tattoo when I was a kid working through college, with no opportunities for road trips in my near future. I continued with my hobby of temporary tattoos. I would try different designs and different locations, and contemplate which colors worked best with my fair skin...
Anyhoo as I was pondering my future tattoo, I was working in our local hospital. One day as I was helping a woman who was the same age as my grandma have her sponge bath, I noticed something on her belly. At first I thought some jello or something had gotten on her and dried. So, I tried to help wash it off. Only it didn't come off. Then I realized it was a TATTOO! Of a ROSE! A withered, disfigured, faded rose. I was quite shocked. Here was this sweet little old lady with a TATTOO on her belly! What made it even worse was that the tattoo wasn't SUPPOSED to be on her belly. It was supposed to be about 12 inches farther north. Sadly, as her body began to sag and shift, her once perky rose tattoo was now a sad and saggy shriveled blob.
I never did get a tattoo. Every time I thought about getting a tattoo after that, I would picture that disturbing image.
Now when I see everyone running around with tattoos, I'm really glad I never got one. Not because I care that they have tattoos. I had wanted a tattoo as a statement of being different. If I had one now, I'd just be like everyone else. And where's the fun in that?
When I have veterans in as patients, I always look at their tattoos, and ask them about them. Some of them are embarrassed, but most of them have an interesting tale to tell about getting it. I have to say one of the perks about being a nurse, is the ability to ask darn near anything of people, and they answer the questions as if you have every right to know...
I remember a few years ago, I was trying to start an IV on an elderly gentleman who had a tattoo on his forearm. He had come in dressed as many men his age do: Docker pants, button up shirt, sweater vest, gold watch and fedora in place. I love when men come in dressed like this as it is very similar to how my Grandad Marvin dressed. Anyway, he was out of his "civilian clothes" and had changed into our very flattering "one size fits none" hospital gown. I had tucked him up in warm blankets, and gathered my supplies for his IV.
I placed the tourniquet on his upper arm, and began my survey for a likely vein candidate, I vaguely noticed he had a tattoo. Typical of elderly people, his skin was loose and thin. I stretched it taunt to see if I had any takers pop up. I couldn't help myself, but I started to chuckle as I stretched his skin out and realized that he had the oh so classic naked lady tattoo on his forearm. He asked me what I was laughing at.
"I'm sorry. I just couldn't help but think that I bet when you got that naked lady tattoo you never dreamed she'd get old and saggy along with you!"
Fortunately, he saw the humor in the situation along with me.
I got my first tattoo in 1993. I was a Junior in high school.
And it wasn't real.
You see, it was a very classy rub on tattoo. I think I got it from Claire's. I loved it. I proudly sported it on my ankle, just above my bobby sock during basketball season so everyone could admire it's beauty in my cheerleading uniform.
The thing about rub on tattoos is they come off. So a few days later I put a butterfly tattoo on my OTHER ankle. It was sooooo beautiful. I think it was a big blue butterfly. But I could be mistaken.
"Do you know what people think of you when they see those tattoos on your legs?" my mom would ask.
"They think it's in a different location every time they see it," was my smart reply. (I fear I frequently needed my face smacked in high school.)
So in high school I had a love affair with tattoos. I would put them on my shoulders if I knew I was going to wear a sleeveless shirt, but I quickly learned they weren't as pretty as the ones I put on my legs, due to my resistance to shaving my arms...
In those days tattoo parlors were illegal in Oklahoma. I turned 18 in 1993, and I think my parents were quite relieved that I could not just wander up the street and get a REAL tattoo. However, I was determined that one day I would have a tattoo. I hadn't settled on the exact design, or even location. You see, NOBODY had tattoos in those days. Well, unless you were a biker, active military, or a veteran. But other than that, no all American girls had tattoos. However, for some reason I had determined it was my destiny to decorate my body with colored ink.
I graduated high school in 1994. That May I went to work at a regional hospital in our area as a nurse's aide. I did all of those things that nurses receive such glory for. You know: Bed baths, toileting, diaper changing, spoon feeding, and lets not forget overall cleaner of vomit. I always tell people who are considering nursing as a profession to work as an aide before they do it. If you can do the most menial part of the job and still love it, then it is definitely your calling.
So there I was 18 years old, working as a nurse's aide and pondering the exact location of my permanent tattoo, and how I was going to manage to get said tattoo when I was a kid working through college, with no opportunities for road trips in my near future. I continued with my hobby of temporary tattoos. I would try different designs and different locations, and contemplate which colors worked best with my fair skin...
Anyhoo as I was pondering my future tattoo, I was working in our local hospital. One day as I was helping a woman who was the same age as my grandma have her sponge bath, I noticed something on her belly. At first I thought some jello or something had gotten on her and dried. So, I tried to help wash it off. Only it didn't come off. Then I realized it was a TATTOO! Of a ROSE! A withered, disfigured, faded rose. I was quite shocked. Here was this sweet little old lady with a TATTOO on her belly! What made it even worse was that the tattoo wasn't SUPPOSED to be on her belly. It was supposed to be about 12 inches farther north. Sadly, as her body began to sag and shift, her once perky rose tattoo was now a sad and saggy shriveled blob.
I never did get a tattoo. Every time I thought about getting a tattoo after that, I would picture that disturbing image.
Now when I see everyone running around with tattoos, I'm really glad I never got one. Not because I care that they have tattoos. I had wanted a tattoo as a statement of being different. If I had one now, I'd just be like everyone else. And where's the fun in that?
When I have veterans in as patients, I always look at their tattoos, and ask them about them. Some of them are embarrassed, but most of them have an interesting tale to tell about getting it. I have to say one of the perks about being a nurse, is the ability to ask darn near anything of people, and they answer the questions as if you have every right to know...
I remember a few years ago, I was trying to start an IV on an elderly gentleman who had a tattoo on his forearm. He had come in dressed as many men his age do: Docker pants, button up shirt, sweater vest, gold watch and fedora in place. I love when men come in dressed like this as it is very similar to how my Grandad Marvin dressed. Anyway, he was out of his "civilian clothes" and had changed into our very flattering "one size fits none" hospital gown. I had tucked him up in warm blankets, and gathered my supplies for his IV.
I placed the tourniquet on his upper arm, and began my survey for a likely vein candidate, I vaguely noticed he had a tattoo. Typical of elderly people, his skin was loose and thin. I stretched it taunt to see if I had any takers pop up. I couldn't help myself, but I started to chuckle as I stretched his skin out and realized that he had the oh so classic naked lady tattoo on his forearm. He asked me what I was laughing at.
"I'm sorry. I just couldn't help but think that I bet when you got that naked lady tattoo you never dreamed she'd get old and saggy along with you!"
Fortunately, he saw the humor in the situation along with me.
Tuesday, January 10, 2012
Putting A Face To It
Today I received an order from one of our kidney doctors to remove a dialysis catheter from one of his patients. "I don't know why Southwest left this line in when they discharged him a few days ago. It needs to come out." The line is one we consider temporary, and not safe to be left in outside of the hospital as it is only held in by a stitch, and if it comes out the patient could bleed to death if proper pressure is not applied.
Just another day in the world of health care...
I had the patient come to our department after his dialysis treatment. I noted that he was Mexican. I asked if he spoke English and he said "Yes." I asked what his plans were for dialysis if I removed his access. He simply shrugged. After a brief interview I realized that he was not sure if he still needed dialysis, and if he did, he was not sure how he was going to receive it.
"Are you supposed to go home today?"
He said yes he was, but still didn't have an answer how he was supposed to get treatment. I pulled up his chart on the computer and looked up the note from his doctor.
I was startled at what I found, but I could understand the reasoning behind it...
I had just never found myself in the position of explaining such things to a patient. After a moment's thought, I read the following doctor's note aloud to the patient:
Patient is an undocumented worker from Mexico. I instructed patient that he needs to return to Mexico where he can get health care, and continue treatment for his renal failure. I also told patient that if he develops shortness of breath, he needs to return to the nearest hospital where he will be treated for his renal failure.
The patient became very reserved and stoic after I read the note aloud to him. I asked if he understood what the doctor was saying.
He shrugged and avoided eye contact with me. I wondered what he was thinking. I wondered what he thought I was thinking. Did he think I felt he didn't deserve health care because he does not have the proper paper work? My reality is that even if he didn't have paper work, as a laborer, odds are he wouldn't have insurance. Of course, our state Medicaid system would step in if he were a legal citizen. Instead, this man has a serious, terminal if not treated illness, and no means to get it paid for. I quietly stood beside him and thought about his situation and the consequences. I wondered if he was able to fully grasp what was going to happen with him, considering his not quite fluent English. How do I explain what he is facing? What do I say to a man that I know is doomed to death if he does not receive treatment?
Sometimes there are just no words to say.
After what felt like an eternity of silence, I asked him if he understood what it meant to lose function of his kidneys. Again, he shrugged.
"Juan, once you've lost function of your kidneys, it usually means that it's permanent. They are no longer able to clean out your blood of toxins and fluid. Those toxins and fluids build up and you end up back in the hospital, unable to breathe. The best thing you can do at this point is dialysis, which is what we've been doing. Unfortunately, you don't have insurance, and you can't get insurance because you're not a legal citizen. That is why Dr. K is suggesting you return to Mexico."
Of course he continued to look straight ahead, and barely acknowledge what I was saying.
"Has anyone talked to you about monitoring how much you drink and changes in what you eat?" He didn't remember if they did.
I don't doubt that he has been instructed on both of those things. I just don't think he really understood what he needed to do. I tried to explain the importance of watching his fluid intake. I talked about avoiding the salt shaker. At first I thought he was not going to engage in the conversation. He surprised me by asking how much he could safely drink in a day. I told him that it varies from patient to patient, and he needed to ask Dr. K. "However, a pretty basic measure is not over two liters."
Of course he had no clear idea of liters. I told him to think of a big bottle of pop, and I got a foam cup and told him to not drink over nine of those a day. We discussed that he has to consider liquid from soups, jello, ice cream and even ice. I gave the lecture on no soda and certainly no alcohol. He told me he doesn't drink "cerveza" and I told him I hoped that was so.
I removed his dialysis catheter with a heavy heart. My mind was spinning with things he needed to know to have any hope of controlling this disease without dialysis. And yet, I realize that all of those things are really just tiny bandages on a huge gaping wound. After I removed his catheter I reminded him to leave the dressing on for at least one day. I reminded him to ask about foods he should avoid, and what level he should keep his fluid intake at. When I called report, his nurse was off the floor. I asked the nurse taking report for him to please have her get a dietary consult so the patient can have a better idea of what foods would be safe to eat.
After leaving Juan's bedside, I went to my next patient. Also of Mexican decent. She speaks little to no English, and instead of removing, I was assisting in PLACING a permanent dialysis catheter. She will go home and receive dialysis three times a week, four hours each day...And it will all be paid for by the tax payers because she is on the state Medicaid program. You see, she is here legally.
Juan is not.
Same disease. Same background. Taxpayers will be picking up the tab for both patients.
I can't get his face out of my mind. He was a quiet man with unexpected green eyes. He was slim and well groomed. After digging through his chart as we chatted I discovered his kidney disease was probably caused by high blood pressure, which he had not realized he had until it was too late. He still did not understand his high blood pressure when I talked to him.
When I'm outside the walls of the hospital it is easy to say that we have to stop giving health care to all of these illegals. It's easy to complain about the drain on our budget that their children are, because they all get coverage. However, when you are looking in the face of that person, and you know that they will surely die without proper care it is a big pill to swallow.
Of course, I realize Juan is still getting health care. And, he's getting it for "free" as there is probably no way he will be able to pay, and no way for us to collect.
I was physically ill as I spoke to him. His condition will only get worse. He will continue to go into a crisis of fluid overload. This will cause him to either go to the hospital where he can get a temporary dialysis catheter placed like the one I removed today and receive a few treatments until he's "stable" and the doctor can discharge him and try not to let him weigh on too heavily on his already overburdened conscience. (After all, any doctor that works for our hospital is not in it for the money. We are known for giving away free health care.) Or, Juan will literally drown in his own body fluid because his heart will be overloaded with fluid and literally give out from inability to deal with the fluid. If by some miracle he is able to manage his fluid intake without dialysis, his kidneys will not be able to manage the waste products and his potassium levels will become so critically high that he will die from cardiac arrest...
So that sucks.
He will continue to be a drain on the system, getting "free health care" because no hospital will turn him away. This is not near to the cost if he actually received dialysis three times a week, four hours at a time like he probably needs. But it will still be a cost to the taxpayer. This sporadic treatment given as a result of recurring crisis will take it's toll on his body, and his kidney disease will progress rapidly.
And then he will die.
So that sucks even more.
As I spoke to Juan today I realized that putting a face to something changes your perspective. I'm not saying that illegals should all get free health care. That would just be crazy. What I will say is that it's a lot easier to say "kick 'em out of the country" when you're talking about a nameless, faceless person. What will happen to him if he returns to Mexico? Will he get treatment? I can't imagine that he will get the level he would here. I imagine he would be treated from one crisis situation to the next.
But maybe I'm wrong.
All I know is that he is a man. A human being with a family and friends and hopes and dreams of a better life. He is a creation of God. He has a scary diagnosis that I don't think he understands. I pray for his safety.
Just another day in the world of health care...
I had the patient come to our department after his dialysis treatment. I noted that he was Mexican. I asked if he spoke English and he said "Yes." I asked what his plans were for dialysis if I removed his access. He simply shrugged. After a brief interview I realized that he was not sure if he still needed dialysis, and if he did, he was not sure how he was going to receive it.
"Are you supposed to go home today?"
He said yes he was, but still didn't have an answer how he was supposed to get treatment. I pulled up his chart on the computer and looked up the note from his doctor.
I was startled at what I found, but I could understand the reasoning behind it...
I had just never found myself in the position of explaining such things to a patient. After a moment's thought, I read the following doctor's note aloud to the patient:
Patient is an undocumented worker from Mexico. I instructed patient that he needs to return to Mexico where he can get health care, and continue treatment for his renal failure. I also told patient that if he develops shortness of breath, he needs to return to the nearest hospital where he will be treated for his renal failure.
The patient became very reserved and stoic after I read the note aloud to him. I asked if he understood what the doctor was saying.
He shrugged and avoided eye contact with me. I wondered what he was thinking. I wondered what he thought I was thinking. Did he think I felt he didn't deserve health care because he does not have the proper paper work? My reality is that even if he didn't have paper work, as a laborer, odds are he wouldn't have insurance. Of course, our state Medicaid system would step in if he were a legal citizen. Instead, this man has a serious, terminal if not treated illness, and no means to get it paid for. I quietly stood beside him and thought about his situation and the consequences. I wondered if he was able to fully grasp what was going to happen with him, considering his not quite fluent English. How do I explain what he is facing? What do I say to a man that I know is doomed to death if he does not receive treatment?
Sometimes there are just no words to say.
After what felt like an eternity of silence, I asked him if he understood what it meant to lose function of his kidneys. Again, he shrugged.
"Juan, once you've lost function of your kidneys, it usually means that it's permanent. They are no longer able to clean out your blood of toxins and fluid. Those toxins and fluids build up and you end up back in the hospital, unable to breathe. The best thing you can do at this point is dialysis, which is what we've been doing. Unfortunately, you don't have insurance, and you can't get insurance because you're not a legal citizen. That is why Dr. K is suggesting you return to Mexico."
Of course he continued to look straight ahead, and barely acknowledge what I was saying.
"Has anyone talked to you about monitoring how much you drink and changes in what you eat?" He didn't remember if they did.
I don't doubt that he has been instructed on both of those things. I just don't think he really understood what he needed to do. I tried to explain the importance of watching his fluid intake. I talked about avoiding the salt shaker. At first I thought he was not going to engage in the conversation. He surprised me by asking how much he could safely drink in a day. I told him that it varies from patient to patient, and he needed to ask Dr. K. "However, a pretty basic measure is not over two liters."
Of course he had no clear idea of liters. I told him to think of a big bottle of pop, and I got a foam cup and told him to not drink over nine of those a day. We discussed that he has to consider liquid from soups, jello, ice cream and even ice. I gave the lecture on no soda and certainly no alcohol. He told me he doesn't drink "cerveza" and I told him I hoped that was so.
I removed his dialysis catheter with a heavy heart. My mind was spinning with things he needed to know to have any hope of controlling this disease without dialysis. And yet, I realize that all of those things are really just tiny bandages on a huge gaping wound. After I removed his catheter I reminded him to leave the dressing on for at least one day. I reminded him to ask about foods he should avoid, and what level he should keep his fluid intake at. When I called report, his nurse was off the floor. I asked the nurse taking report for him to please have her get a dietary consult so the patient can have a better idea of what foods would be safe to eat.
After leaving Juan's bedside, I went to my next patient. Also of Mexican decent. She speaks little to no English, and instead of removing, I was assisting in PLACING a permanent dialysis catheter. She will go home and receive dialysis three times a week, four hours each day...And it will all be paid for by the tax payers because she is on the state Medicaid program. You see, she is here legally.
Juan is not.
Same disease. Same background. Taxpayers will be picking up the tab for both patients.
I can't get his face out of my mind. He was a quiet man with unexpected green eyes. He was slim and well groomed. After digging through his chart as we chatted I discovered his kidney disease was probably caused by high blood pressure, which he had not realized he had until it was too late. He still did not understand his high blood pressure when I talked to him.
When I'm outside the walls of the hospital it is easy to say that we have to stop giving health care to all of these illegals. It's easy to complain about the drain on our budget that their children are, because they all get coverage. However, when you are looking in the face of that person, and you know that they will surely die without proper care it is a big pill to swallow.
Of course, I realize Juan is still getting health care. And, he's getting it for "free" as there is probably no way he will be able to pay, and no way for us to collect.
I was physically ill as I spoke to him. His condition will only get worse. He will continue to go into a crisis of fluid overload. This will cause him to either go to the hospital where he can get a temporary dialysis catheter placed like the one I removed today and receive a few treatments until he's "stable" and the doctor can discharge him and try not to let him weigh on too heavily on his already overburdened conscience. (After all, any doctor that works for our hospital is not in it for the money. We are known for giving away free health care.) Or, Juan will literally drown in his own body fluid because his heart will be overloaded with fluid and literally give out from inability to deal with the fluid. If by some miracle he is able to manage his fluid intake without dialysis, his kidneys will not be able to manage the waste products and his potassium levels will become so critically high that he will die from cardiac arrest...
So that sucks.
He will continue to be a drain on the system, getting "free health care" because no hospital will turn him away. This is not near to the cost if he actually received dialysis three times a week, four hours at a time like he probably needs. But it will still be a cost to the taxpayer. This sporadic treatment given as a result of recurring crisis will take it's toll on his body, and his kidney disease will progress rapidly.
And then he will die.
So that sucks even more.
As I spoke to Juan today I realized that putting a face to something changes your perspective. I'm not saying that illegals should all get free health care. That would just be crazy. What I will say is that it's a lot easier to say "kick 'em out of the country" when you're talking about a nameless, faceless person. What will happen to him if he returns to Mexico? Will he get treatment? I can't imagine that he will get the level he would here. I imagine he would be treated from one crisis situation to the next.
But maybe I'm wrong.
All I know is that he is a man. A human being with a family and friends and hopes and dreams of a better life. He is a creation of God. He has a scary diagnosis that I don't think he understands. I pray for his safety.
Wednesday, December 28, 2011
Stress Eating
When a crisis arrives and I'm at home the immediate reaction is to clean the entire house from top to bottom.
When a potential crisis arrives at work, my immediate reaction is to wish I had some fountain Dr. Pepper and Nacho Cheese Doritos.
Yesterday at about 3:30 my supervisor said, "Is Dr. G going to do that ICU patient tonight?"
"What ICU patient? He didn't mention it to me."
"It's that patient that coded this morning. He wants to do her tonight, and he needs anesthesia, but they can't come until after 6."
Well, great. I immediately began needing some Doritos and DP. After all, if she coded odds are she's pretty sick. And I hate dealing with really sick people late in the evening. The rest of the crew has left, and that leaves the call nurse, the doctor and two radiology techs... unless you drag the ICU nurse into the procedure with you...
I went out to ask the doctor if we "had" to do the case that night, or could we wait and do it the next day and we'd book anesthesia...And of course, that would mean our entire department would be there in case things started going south...
He called the attending doctor who responded, "I think her gallbladder is obstructed. If that is the cause of her sepsis, then she won't make it through the night."
Well, crap. I called the anesthesiologist who was immediately annoyed that we were wanting him to put a patient under for a procedure when her labs were terrible, she's on the ventilator, and her blood pressure is still sketchy even though she was on the maximum dose of pressor meds. (Pressor meds are given when a person's blood pressure is too low.)
Oh, I just feel compelled to tell you in an aside note that one time I tried to refuse to do sedation on a very sick patient with Dr. G, because I was almost certain they were going to die on the table. I wanted them to stabilize the patient more before we did the procedure. He looked at me and said, "Andrea, this patient is going to die very soon if we don't do this. So, he can either die with us trying to save him, or we can do nothing and he will still die." What do you say to that? We did the case, and the patient lived. But I swear I carried knots in my neck and shoulders from the stress of that case for weeks afterwards....
After speaking with the anesthesiologist, I reported back to Dr. G that the anesthesiologist said I couldn't bring the patient to our department until he had seen her himself in the ICU. And I was very okay with that...
However, my dad gum doctor just said, "That's okay. I'm on my way to the ICU right now. I think we are just going to drain her gallbladder, so I will just need sedation, and you can do that. Come with me."
I could? I didn't WANNA do sedation on this lady! Grrrrrr...I grabbed my DP and chips and headed out the door with him...
(Thankfully, one of the radiology techs that was NOT on call had ran down to the cafeteria and bought me a fountain Dr. Pepper and Cool Ranch Doritos as they were out of Nacho Cheese...She knows me well.)
He and I took off down the hall, sharing my bag of Doritos...Yet, he pointed out that he thinks it's tacky to eat and walk at the same time. I told him to "Shut up and eat a chip." And he did. He knows when he's living dangerously. (By the way, we tell each other to shut up on a regular basis. In fact, I pointed out that I've told him to shut up more than any other human in my life. He said it's ditto for him, unless we count his sister and that took an entire LIFETIME to reach the quantity of shut ups that he's given me. We aren't sure if this is a good thing or not.)
He walked into her room, where three family members were at bedside. He immediately started telling them what we were about to do. As he was talking, I noticed that she was on continuous hemodialysis...This means her kidney function was so poor that they had a machine hooked up pulling her blood out and cleaning it continuously. I then noticed that her blood pressure was 66/47.
YIKES!!!
I immediately went to find the ICU nurse and tell her that if I had to take this patient and sedate her, then she was darn well coming with me. And to shove a few more Doritos in my mouth and suck down some more liquid Xanax...Well, fortunately, the nurse had already talked to the attending and convinced her that the patient would probably not survive the transfer to our department and subsequent sedation. She told Dr. G this, and asked if there was any way possible he could put the drain in at bedside.
"Sure. We can try that."
How do you spell relief?
Well, we put the drain in at bedside, and the poor woman hurt tremendously as we did it, because her blood pressure was too low to give her anything to ease the pain. The doctor kept asking us to give her something for pain, but the ICU nurse was adding a new pressor med, and another ICU nurse had joined us for moral support, (and to hold her down because it really did hurt,) and we were all presenting a united "refusal to give pain medicine" front...So, it hurt her really really badly. But she lived through the procedure.
Dr. G said this is the first time he's drained a gallbladdder without giving some serious meds to get through it. The three of us just put on our callus nurse faces and said, "Well, now you can check that off your list." And we all thanked each other for the good work, and I went home, slurping on my drink and wishing I hadn't shared the last of my chips with the doctor...
So, what do you want to eat when you are stressed? Do you eat at all? Do you go into a frenzy of activity? Perhaps you curl into the fetal position and stare at the ceiling fan...
When a potential crisis arrives at work, my immediate reaction is to wish I had some fountain Dr. Pepper and Nacho Cheese Doritos.
Yesterday at about 3:30 my supervisor said, "Is Dr. G going to do that ICU patient tonight?"
"What ICU patient? He didn't mention it to me."
"It's that patient that coded this morning. He wants to do her tonight, and he needs anesthesia, but they can't come until after 6."
Well, great. I immediately began needing some Doritos and DP. After all, if she coded odds are she's pretty sick. And I hate dealing with really sick people late in the evening. The rest of the crew has left, and that leaves the call nurse, the doctor and two radiology techs... unless you drag the ICU nurse into the procedure with you...
I went out to ask the doctor if we "had" to do the case that night, or could we wait and do it the next day and we'd book anesthesia...And of course, that would mean our entire department would be there in case things started going south...
He called the attending doctor who responded, "I think her gallbladder is obstructed. If that is the cause of her sepsis, then she won't make it through the night."
Well, crap. I called the anesthesiologist who was immediately annoyed that we were wanting him to put a patient under for a procedure when her labs were terrible, she's on the ventilator, and her blood pressure is still sketchy even though she was on the maximum dose of pressor meds. (Pressor meds are given when a person's blood pressure is too low.)
Oh, I just feel compelled to tell you in an aside note that one time I tried to refuse to do sedation on a very sick patient with Dr. G, because I was almost certain they were going to die on the table. I wanted them to stabilize the patient more before we did the procedure. He looked at me and said, "Andrea, this patient is going to die very soon if we don't do this. So, he can either die with us trying to save him, or we can do nothing and he will still die." What do you say to that? We did the case, and the patient lived. But I swear I carried knots in my neck and shoulders from the stress of that case for weeks afterwards....
After speaking with the anesthesiologist, I reported back to Dr. G that the anesthesiologist said I couldn't bring the patient to our department until he had seen her himself in the ICU. And I was very okay with that...
However, my dad gum doctor just said, "That's okay. I'm on my way to the ICU right now. I think we are just going to drain her gallbladder, so I will just need sedation, and you can do that. Come with me."
I could? I didn't WANNA do sedation on this lady! Grrrrrr...I grabbed my DP and chips and headed out the door with him...
(Thankfully, one of the radiology techs that was NOT on call had ran down to the cafeteria and bought me a fountain Dr. Pepper and Cool Ranch Doritos as they were out of Nacho Cheese...She knows me well.)
He and I took off down the hall, sharing my bag of Doritos...Yet, he pointed out that he thinks it's tacky to eat and walk at the same time. I told him to "Shut up and eat a chip." And he did. He knows when he's living dangerously. (By the way, we tell each other to shut up on a regular basis. In fact, I pointed out that I've told him to shut up more than any other human in my life. He said it's ditto for him, unless we count his sister and that took an entire LIFETIME to reach the quantity of shut ups that he's given me. We aren't sure if this is a good thing or not.)
He walked into her room, where three family members were at bedside. He immediately started telling them what we were about to do. As he was talking, I noticed that she was on continuous hemodialysis...This means her kidney function was so poor that they had a machine hooked up pulling her blood out and cleaning it continuously. I then noticed that her blood pressure was 66/47.
YIKES!!!
I immediately went to find the ICU nurse and tell her that if I had to take this patient and sedate her, then she was darn well coming with me. And to shove a few more Doritos in my mouth and suck down some more liquid Xanax...Well, fortunately, the nurse had already talked to the attending and convinced her that the patient would probably not survive the transfer to our department and subsequent sedation. She told Dr. G this, and asked if there was any way possible he could put the drain in at bedside.
"Sure. We can try that."
How do you spell relief?
Well, we put the drain in at bedside, and the poor woman hurt tremendously as we did it, because her blood pressure was too low to give her anything to ease the pain. The doctor kept asking us to give her something for pain, but the ICU nurse was adding a new pressor med, and another ICU nurse had joined us for moral support, (and to hold her down because it really did hurt,) and we were all presenting a united "refusal to give pain medicine" front...So, it hurt her really really badly. But she lived through the procedure.
Dr. G said this is the first time he's drained a gallbladdder without giving some serious meds to get through it. The three of us just put on our callus nurse faces and said, "Well, now you can check that off your list." And we all thanked each other for the good work, and I went home, slurping on my drink and wishing I hadn't shared the last of my chips with the doctor...
So, what do you want to eat when you are stressed? Do you eat at all? Do you go into a frenzy of activity? Perhaps you curl into the fetal position and stare at the ceiling fan...
Tuesday, November 1, 2011
Taking Thoroughness One Step Beyond..
Attention: I actually wrote this post last week, but never posted it. I just felt I should confess that this story is late...
I feel better now.
I'm learning to not worry if I'm going to be "short hours" at work because I took a few days off for Fall Break...
God provides plenty of make up hours for me...
In the form of a ten hour, no lunch shift on Monday followed by an eleven hour shift on Tuesday. On Tuesday I did get lunch, but I took it around eleven or eleven thirty, and believe me that by the time I was clocking out at 7:30, I felt as if I had not received lunch at all...
So, following my whining about hours, I have a nursing story for you...
And it's not a fun story. I can't even begin to describe the stress and fear and overall sense of sadness I had with the case that is still fresh in my mind...
So instead of sharing a scary, "why am I a nurse" story, I will instead tell you of a conversation that was overheard on Tuesday.
I work with a nurse who could be described as OCD. And that would not be an overstatement. We had a long line of patients backed up due to some urgent add on cases, and a delay with an anesthesiologist for a case my doctor was doing in surgery, followed by difficulty with the case causing it to run over. Consequently we had more than adequate time to prep our patients for their procedures...
Well, OCD nurse can make a fifteen minute duty last two hours if given the chance. He has this tendency to create work when there's none to be done when he has too much time on his hands. Strangely, he seems to stress himself out when he has too much time also. He spent two solid hours getting his patient ready. He even went over discharge instructions before the procedure began, which is actually pretty normal, but it's usually a brief description of what to expect after the procedure and a list of a few restrictions along with a handout. He was telling his patient not to drive as she was going to receive sedation. This woman was over 80 years old and no longer drove...And she told OCD nurse so..."Well, I'm just saying you need to be careful about operating any equipment or electronics today. For example if you have an electric can opener at home, you might want to avoid using it today."
????
Needless to say, we haven't let him live that statement down, and I don't think we will any time soon.
BEWARE THE ELECTRIC CAN OPENER!!!
I feel better now.
I'm learning to not worry if I'm going to be "short hours" at work because I took a few days off for Fall Break...
God provides plenty of make up hours for me...
In the form of a ten hour, no lunch shift on Monday followed by an eleven hour shift on Tuesday. On Tuesday I did get lunch, but I took it around eleven or eleven thirty, and believe me that by the time I was clocking out at 7:30, I felt as if I had not received lunch at all...
So, following my whining about hours, I have a nursing story for you...
And it's not a fun story. I can't even begin to describe the stress and fear and overall sense of sadness I had with the case that is still fresh in my mind...
So instead of sharing a scary, "why am I a nurse" story, I will instead tell you of a conversation that was overheard on Tuesday.
I work with a nurse who could be described as OCD. And that would not be an overstatement. We had a long line of patients backed up due to some urgent add on cases, and a delay with an anesthesiologist for a case my doctor was doing in surgery, followed by difficulty with the case causing it to run over. Consequently we had more than adequate time to prep our patients for their procedures...
Well, OCD nurse can make a fifteen minute duty last two hours if given the chance. He has this tendency to create work when there's none to be done when he has too much time on his hands. Strangely, he seems to stress himself out when he has too much time also. He spent two solid hours getting his patient ready. He even went over discharge instructions before the procedure began, which is actually pretty normal, but it's usually a brief description of what to expect after the procedure and a list of a few restrictions along with a handout. He was telling his patient not to drive as she was going to receive sedation. This woman was over 80 years old and no longer drove...And she told OCD nurse so..."Well, I'm just saying you need to be careful about operating any equipment or electronics today. For example if you have an electric can opener at home, you might want to avoid using it today."
????
Needless to say, we haven't let him live that statement down, and I don't think we will any time soon.
BEWARE THE ELECTRIC CAN OPENER!!!
Monday, October 3, 2011
If I Only Had a Brain
I am about to attempt to tell you a work story. It is a story which could be very complicated and difficult to portray if you aren't a part of the medical field. But if you will just suffer through and try to see my sheer idiocy, I think you will appreciate it.
This week we have been taking care of a lady who has been in the icu for over two weeks now. She suffered a hemmorhagic stroke and the neurosurgeon went in to clip the bleed. After surgery she was completely unresponsive. No reflexes noted. Her eyes are open but they jerk around, never really seeing anything. She is on a ventilator, and she initiates breath, but is unable to fully breathe on her own. Her heart is stable. She has a giant tube coming out the top of her head to drain the excess fluid off, and she has a pressure sensor in there to monitor her intracranial pressure (referred to ICP from this point on.) She also has staples across half of her head where they went in to do the surgery on her brain. Her feet and hands are cold and mottled, and her limbs are limp with no muscle tone response noted when you move or reposition her.
This is all very horrific sounding, I know. It is horrific. Especially when you factor in that the patient's family is English as a second language, and they keep thinking she's going to get better. I don't see how she's going to get better after two weeks of no response, but I'm not God and that's not my decision to make. Instead, I just feel terrible for them.
Here's a news flash for you: I hate brains. I love things to do with the heart and cardiovascular system. I get it. I specialized in it right out of school, and while neurologic issues have never been completely unavoidable, since I've been in my current job they have been few and far between. Imagine my joy when I realized on Monday that I was going to have to bring this patient from the intensive care unit to our department and monitor her while the doctor did a cerebral angiogram, which is basically a study of the vessels in her brain. I got a quick and dirty inservice from the patient's nurse about her drains and what they meant, and especially that her ICP must not get above 20, and her drain needed to stay at the level of her ear. If the drain was repositioned during transport and was above her ear, it wouldn't drain. Too far below the ear, and it would drain too fast.
How do I spell stress? B-R-A-I-N.
Monday we did the procedure with no hitches. We injected some medicine directly into her brain that was supposed to improve blood flow to her brain. I was annoyed to learn that we would be bringing her back daily until she gets better.
So we had to bring her back on Tuesday. On Tuesday I went with one of my nurse friends for our department, and we had agreed to tag team her. I was feeling pretty okay with it, as the previous day had gone fine.
Well, of course by the time I moved her to our table and got my monitor hooked up, and the respiratory therapist put her on a portable ventilator, her ICP had climbed to 28. "Well crap." But then as I looked through her chart I realized that it said to notify the doctor if the ICP stayed up more than 10 minutes. So I waited a bit.
Her ICP didn't budge...I lowered the drain...it still didn't budge, nor did it begin to drain. I started to sweat. Profusely. I was so glad I had another nurse assisting me, and our plan was for her to stay with the patient and do basic care, and I would fetch anything she needed, or call the ICU nurse if she had a question, or whatever needed done...
I paged the neurosurgeon, Dr. X. We will call him Dr. X as his last name has no less than 11 letters and like 5 syllables, and even after talking to him like twenty times I am still not sure how to pronounce it.
So, Dr. X calls back. I inform him of her ICP, her blood pressure, her heart rate, her oxygen levels, and I even was able to tell him what her medications were running at. I was mentally patting myself on the back for having facts, even as I felt sweat trickling between my shoulder blades.
"What is her ventriculostomy pressure?"
Now, this doctor has a pretty strong accent. I was pretty sure I'd misheard him. Because it sounded like he said ventriculostomy, and I was pretty sure no such word existed...So, I said, "Excuse me?"
"Ventriculostomy pressure. What is it?"
"I'm sorry. I can understand ventricul something or other, but that is all."
"Ventriculostomy. Ventriculostomy. Ventriculostomy. What is the pressure reading on it?"
Okay. So he DEFINITELY said ventriculostomy. Which I still felt pretty sure was not a real word. "I'm sorry sir, but I'm not sure what you mean by that." I'm pretty sure that instilled all sorts of confidence in my roll as this patient's care giver.
"On the monitor, what does it say her ventriculostomy pressure is?" Okay. He just keeps saying the same thing over and over. Apparently it's real. And he expects me to know what it is, and what to do about it.
Crapola.
"Sir, I'm sorry, but the only pressure reading I have is off of the Camino, and it says her ICP is 28."
"But there is another monitor coming out of her head. Do you see it?"
WHAT????
"No sir. I only see the Camino pressure monitor and her drain. I will call the ICU nurse to come show me what to do."
"Wait a minute. Aren't you a nurse?"
"Yes sir. I'm a nurse, but to be honest I'm a PROCEDURAL nurse, and while I had Scott give me a quick and dirty report on how to care for this patient, he never said the word ventriculostomy to me."
He then informed me that he had ordered her drain clamped, and that the ICP had probably raised due to the stress of moving, and I simply needed to open the ventriculostomy during the procedure and leave it open for one hour after...
There was that darn WORD again.
So I called the ICU nurse. And it turns out that the ventriculostomy is the drain that I was calling a DRAIN. Because that is what the simple folk call a drain for your brain...a drain. He showed me that he had clamped the drain off the day before, so no matter how low I moved the drain, it wasn't going to lower her ICP. Oh did I mention that I all but put that drain on the floor trying to drop her ICP? Did I mention that by this point my scrubs were soaked in sweat under my lead apron? I told my nurse friend that while I felt incredibly stupid, at least I'd probably never have to meet Dr. X face to face.
Well we opened the drain, and low and behold the ICP dropped to the normal range, and we were able to complete our procedure. After we finished up Dr. X, the neurosurgeon showed up...At least I guessed it was him. He was in a doctor's coat, and he was unfamiliar to me. I could totally tell he was looking for me. I decided to take the bull by the horns.
"Hi! Are you Dr. X?" Sound cheerful and nonchalantly confident Andi. Then he will decide that while you may be a ditz at least you're friendly...
"Yes, I am."
"I'm Andi. I was the nurse on the phone with you earlier. I'm so sorry for the misunderstanding earlier. I don't want you to think we don't know what we're doing here. Except I have never dealt with one of these before. So I guess that means I really don't." And I smiled my most winning smile and I gave a little lighthearted chuckle. Could you just shut up? Why must you blabber on when you are nervous? Or happy? Or sad?
"No problem. I'm sorry too. I thought I was speaking with the ICU nurse, so I was wondering how you didn't know what the monitors were for."
I was so relieved that he wasn't angry, and surprisingly nice but still relatively sure he thought I was a nincompoop...I decided fleeing was the smart thing to do in this situation...I gently lead him to our control room where I introduced him to our doctor, and headed back to the intensive care with the patient.
Of course I ran into Dr. X again before I was gone.
Blast it all! Must this man suddenly be everywhere I have to be?
And I began to blush and sweat even more profusely than I already was..."Hi!" I decided to keep up my light and friendly facade. It wouldn't do at all for him to realize I never wanted to see him again.
"Hello. I wanted to apologize about not realizing where you were earlier..." And he proceeded to take me back to the patient bedside and explain that the ventriculostomy pressure was monitored by a bedside monitor in the ICU, so I really could not have told him that reading as the monitor wasn't with me. And he took the time to explain things to me in a much better detail than the nurse had. And I was able to understand him easier face to face.
That made me feel much better.
And a little bit less of an idiot.
However, I still hate brains...
On a more positive note, I found out that as of January first two neuro interventionalists will be coming to work in our department, and that all of us have to go through special training to know how to care for brain injury patients. I can only begin to guess the sort of ego that comes with a person who is willing to work on brains by inserting a catheter into the artery in your groin and working their way to the brain...And I can only guess this will lead to more interaction with Dr. X...
Oh, wait. That is actually TERRIBLE news. Blast it all.
This week we have been taking care of a lady who has been in the icu for over two weeks now. She suffered a hemmorhagic stroke and the neurosurgeon went in to clip the bleed. After surgery she was completely unresponsive. No reflexes noted. Her eyes are open but they jerk around, never really seeing anything. She is on a ventilator, and she initiates breath, but is unable to fully breathe on her own. Her heart is stable. She has a giant tube coming out the top of her head to drain the excess fluid off, and she has a pressure sensor in there to monitor her intracranial pressure (referred to ICP from this point on.) She also has staples across half of her head where they went in to do the surgery on her brain. Her feet and hands are cold and mottled, and her limbs are limp with no muscle tone response noted when you move or reposition her.
This is all very horrific sounding, I know. It is horrific. Especially when you factor in that the patient's family is English as a second language, and they keep thinking she's going to get better. I don't see how she's going to get better after two weeks of no response, but I'm not God and that's not my decision to make. Instead, I just feel terrible for them.
Here's a news flash for you: I hate brains. I love things to do with the heart and cardiovascular system. I get it. I specialized in it right out of school, and while neurologic issues have never been completely unavoidable, since I've been in my current job they have been few and far between. Imagine my joy when I realized on Monday that I was going to have to bring this patient from the intensive care unit to our department and monitor her while the doctor did a cerebral angiogram, which is basically a study of the vessels in her brain. I got a quick and dirty inservice from the patient's nurse about her drains and what they meant, and especially that her ICP must not get above 20, and her drain needed to stay at the level of her ear. If the drain was repositioned during transport and was above her ear, it wouldn't drain. Too far below the ear, and it would drain too fast.
How do I spell stress? B-R-A-I-N.
Monday we did the procedure with no hitches. We injected some medicine directly into her brain that was supposed to improve blood flow to her brain. I was annoyed to learn that we would be bringing her back daily until she gets better.
So we had to bring her back on Tuesday. On Tuesday I went with one of my nurse friends for our department, and we had agreed to tag team her. I was feeling pretty okay with it, as the previous day had gone fine.
Well, of course by the time I moved her to our table and got my monitor hooked up, and the respiratory therapist put her on a portable ventilator, her ICP had climbed to 28. "Well crap." But then as I looked through her chart I realized that it said to notify the doctor if the ICP stayed up more than 10 minutes. So I waited a bit.
Her ICP didn't budge...I lowered the drain...it still didn't budge, nor did it begin to drain. I started to sweat. Profusely. I was so glad I had another nurse assisting me, and our plan was for her to stay with the patient and do basic care, and I would fetch anything she needed, or call the ICU nurse if she had a question, or whatever needed done...
I paged the neurosurgeon, Dr. X. We will call him Dr. X as his last name has no less than 11 letters and like 5 syllables, and even after talking to him like twenty times I am still not sure how to pronounce it.
So, Dr. X calls back. I inform him of her ICP, her blood pressure, her heart rate, her oxygen levels, and I even was able to tell him what her medications were running at. I was mentally patting myself on the back for having facts, even as I felt sweat trickling between my shoulder blades.
"What is her ventriculostomy pressure?"
Now, this doctor has a pretty strong accent. I was pretty sure I'd misheard him. Because it sounded like he said ventriculostomy, and I was pretty sure no such word existed...So, I said, "Excuse me?"
"Ventriculostomy pressure. What is it?"
"I'm sorry. I can understand ventricul something or other, but that is all."
"Ventriculostomy. Ventriculostomy. Ventriculostomy. What is the pressure reading on it?"
Okay. So he DEFINITELY said ventriculostomy. Which I still felt pretty sure was not a real word. "I'm sorry sir, but I'm not sure what you mean by that." I'm pretty sure that instilled all sorts of confidence in my roll as this patient's care giver.
"On the monitor, what does it say her ventriculostomy pressure is?" Okay. He just keeps saying the same thing over and over. Apparently it's real. And he expects me to know what it is, and what to do about it.
Crapola.
"Sir, I'm sorry, but the only pressure reading I have is off of the Camino, and it says her ICP is 28."
"But there is another monitor coming out of her head. Do you see it?"
WHAT????
"No sir. I only see the Camino pressure monitor and her drain. I will call the ICU nurse to come show me what to do."
"Wait a minute. Aren't you a nurse?"
"Yes sir. I'm a nurse, but to be honest I'm a PROCEDURAL nurse, and while I had Scott give me a quick and dirty report on how to care for this patient, he never said the word ventriculostomy to me."
He then informed me that he had ordered her drain clamped, and that the ICP had probably raised due to the stress of moving, and I simply needed to open the ventriculostomy during the procedure and leave it open for one hour after...
There was that darn WORD again.
So I called the ICU nurse. And it turns out that the ventriculostomy is the drain that I was calling a DRAIN. Because that is what the simple folk call a drain for your brain...a drain. He showed me that he had clamped the drain off the day before, so no matter how low I moved the drain, it wasn't going to lower her ICP. Oh did I mention that I all but put that drain on the floor trying to drop her ICP? Did I mention that by this point my scrubs were soaked in sweat under my lead apron? I told my nurse friend that while I felt incredibly stupid, at least I'd probably never have to meet Dr. X face to face.
Well we opened the drain, and low and behold the ICP dropped to the normal range, and we were able to complete our procedure. After we finished up Dr. X, the neurosurgeon showed up...At least I guessed it was him. He was in a doctor's coat, and he was unfamiliar to me. I could totally tell he was looking for me. I decided to take the bull by the horns.
"Hi! Are you Dr. X?" Sound cheerful and nonchalantly confident Andi. Then he will decide that while you may be a ditz at least you're friendly...
"Yes, I am."
"I'm Andi. I was the nurse on the phone with you earlier. I'm so sorry for the misunderstanding earlier. I don't want you to think we don't know what we're doing here. Except I have never dealt with one of these before. So I guess that means I really don't." And I smiled my most winning smile and I gave a little lighthearted chuckle. Could you just shut up? Why must you blabber on when you are nervous? Or happy? Or sad?
"No problem. I'm sorry too. I thought I was speaking with the ICU nurse, so I was wondering how you didn't know what the monitors were for."
I was so relieved that he wasn't angry, and surprisingly nice but still relatively sure he thought I was a nincompoop...I decided fleeing was the smart thing to do in this situation...I gently lead him to our control room where I introduced him to our doctor, and headed back to the intensive care with the patient.
Of course I ran into Dr. X again before I was gone.
Blast it all! Must this man suddenly be everywhere I have to be?
And I began to blush and sweat even more profusely than I already was..."Hi!" I decided to keep up my light and friendly facade. It wouldn't do at all for him to realize I never wanted to see him again.
"Hello. I wanted to apologize about not realizing where you were earlier..." And he proceeded to take me back to the patient bedside and explain that the ventriculostomy pressure was monitored by a bedside monitor in the ICU, so I really could not have told him that reading as the monitor wasn't with me. And he took the time to explain things to me in a much better detail than the nurse had. And I was able to understand him easier face to face.
That made me feel much better.
And a little bit less of an idiot.
However, I still hate brains...
On a more positive note, I found out that as of January first two neuro interventionalists will be coming to work in our department, and that all of us have to go through special training to know how to care for brain injury patients. I can only begin to guess the sort of ego that comes with a person who is willing to work on brains by inserting a catheter into the artery in your groin and working their way to the brain...And I can only guess this will lead to more interaction with Dr. X...
Oh, wait. That is actually TERRIBLE news. Blast it all.
Saturday, September 3, 2011
What I Do
I'm a nurse. I know. News flash, right?
I've been thinking about it all week. It's been one of those "Why am I a nurse?" and "I love being a nurse" week.
I've been thinking of all that transpired this week, and I've been thinking it seems that there should be a blog in there somewhere, but I'm not sure I can convey the angst and beauty I've experienced this week.
Monday night I was on call and we worked on one patient for nearly four hours. Her pain was out of control due to advanced cancer and I gave that woman more medicine than I've ever given one human being. More than I felt was probably safe, but what do you do when your patient is weeping and jerking all over the table during a very delicate procedure and she is crying out to God? You look at your doctor who tells you to give her more medicine and you do it.
I called and checked on her first thing Tuesday morning, then talked to her family on Wednesday. They all said that she had been anxious all Monday night and didn't sleep at all. While that is sad, I was relieved I didn't kill her with the quantity of meds and variety I had been pumping in her trying to get her comfortably through the procedure.
Tuesday we had a patient who has been with us for a while come in. She is dying of liver cancer. Her granddaughter had brought her in for one last drainage of the fluid collection on her abdomen that often results from liver diseases. I was afraid she was going to die before I got her from the wheelchair to the stretcher. I asked "Tiffany" how she was able to get her to the car and then to the wheelchair to come to our department. She confessed she just hugged her and total lifted her. The patient's heart rate was in the 130s-160 and she was not making eye contact. She would answer questions slowly and laboriously. I sat down and asked Tiffany if she wanted me to transfer her grandmother to the ER or take her home to die. She decided to take her home. We sat in the hall and I held her while she cried. Tiffany is about my age and has a beautiful little boy that she takes with her everywhere she takes her grandmother. She kept her grandmother beautifully groomed with lovely hair, and manicured toes and fingers. I told Tiffany that she is one of the bravest women I've ever met. I was proud of what she had chosen to do for her grandmother. I know she'll never regret that decision to care for her grandmother. It has not been easy. But I know it was the right thing for her to do, and you could see the love they had for each other every time my patient would speak of her precious granddaughter.
Later in the day on Tuesday we had an urgent case added. The patient had an obstruction between her kidney and bladder, so her right kidney was not draining urine. Consequently this eighty something year old woman was in pain. The pain medicine had made her very confused and combative. When I got her, the doctor pointed out that the key to this procedure was going to be speed. We had to put her on her belly on a table not much wider than an ironing board and convince her to lie still while the doctor placed a tube through the skin and into the kidney to relieve the pressure. One of my fellow nurses told me, "I don't have a good feeling about this." I was surprised because while I was worried about how we were going to get her settled into position, I wasn't worried worried...Like the "not good feeling" worried.
I did express concern to the doctor that she was going septic, which simply means that there is an infection in her blood, and it goes systemic, and can have very scary results. He said "Okay, but we have to get this tube in to fix it." I agreed.
Well, after we used four staff members to wrestle a 50 kilogram woman onto the table, tied her hands and feet, and I gently medicated her, with the age and weight burdening my brain, she finally settled down. My doctor worked like a fiend and had the tube in within a five minutes.
However, her blood pressure plummeted...
She went unresponsive. We flipped her over onto the stretcher and I gave her reversals for the meds I'd given her, hoping it was a case of skinny frail white woman receiving too much sedation, even though I'd barely given her anything.
No response.
Of course her IV went bad. The good news with that was that she had beautiful veins, the kind nurses look on lustfully when they pass by you...And since she was now calm, I got a new IV in no problem. I gave her more reversals. Still no response. I started pumping her full of fluids and called in a "rapid response" which basically gets the Code Team there before a full code actually happens...
She came around a little. She began to answer questions and her pressure recovered a bit. Not enough to relax us, but a bit. We got her placed in the intensive care unit. By the time the rush was over, her son and daughter in law had went to her original room on a medical/surgical unit to get her belongings. I hated that I missed them. I had prayed with them before the procedure and reassured her daughter in law that we would take good care of her. We talked about God being in control and caring about all of our worries. We prayed that they would have peace and that the patient would be calm for the procedure. I don't know how they felt. I'm sure they were scared when they heard the call for assistance over the hospital PA. I wish I had caught up with them Wednesday to chat with them and learn how their loved one was. I wish I had sought them out at the end of the day on Tuesday to hug their necks and tell them I was sorry for their family member's illness.
But I didn't. And there wasn't even any reason not to. I was completely bored on Wednesday. So bored that a fellow nurse and I decided to do the eleven flights of stairs up and down (of course, why would we stay on the roof?) and do ten sets of squats at each landing. Then a few hours later we did it again. All I did to earn my paycheck was audit old charts and stock carts, call patients lined up for the next week, and make sure everything was neat and tidy. And while all of that needed done, it isn't what I really visualize myself doing when I head to work in the morning. I finished off my day with a four hour mandatory class. Again, not what I think of doing when I am at work.
So really there was no reason to not follow up with my little lady. I just didn't. I guess the difference with her was that whatever was wrong with her, I had no control over, yet it was a relatively expected outcome. It was all part of the pathology of her illness. I knew that, and wasn't overly surprised when events panned out like they did. Whereas the first patient had metastatic cancer, but what I was doing to her was way out of my comfort zone.
In each case I was doing what I felt was best and what I knew to do. The difference between the first and the last is back up. In the call case we were there until late in the evening, and I really didn't have a lot of people to bounce off ideas about what to do, and what else I could try to get her pain under control. The second case was during the middle of the day, and two other nurses from my department were right there talking things out with me, discussing what we should try next, and the doctor was able to get on the phone to the patient's attending physician.
So.
I'm a nurse. It's weird. Sometimes I wonder why I do it. I especially wonder what is wrong with me to love doing it. Especially as I'm sitting here typing with a headache that is directly tied to they tension I've been carrying in my neck and shoulders this week.
But I do it. I love doing it, and on some weird level I would love it if my girls did it too. We could have that weird nurse bond that commiserates about annoying, smelly patients and gripey needy doctors. We could swap horror stories of blood squirting and vomit flying...And we could commiserate over each others mistakes, and the wish we had done it different cases...
I'm a nurse.
It's what I do.
I've been thinking about it all week. It's been one of those "Why am I a nurse?" and "I love being a nurse" week.
I've been thinking of all that transpired this week, and I've been thinking it seems that there should be a blog in there somewhere, but I'm not sure I can convey the angst and beauty I've experienced this week.
Monday night I was on call and we worked on one patient for nearly four hours. Her pain was out of control due to advanced cancer and I gave that woman more medicine than I've ever given one human being. More than I felt was probably safe, but what do you do when your patient is weeping and jerking all over the table during a very delicate procedure and she is crying out to God? You look at your doctor who tells you to give her more medicine and you do it.
I called and checked on her first thing Tuesday morning, then talked to her family on Wednesday. They all said that she had been anxious all Monday night and didn't sleep at all. While that is sad, I was relieved I didn't kill her with the quantity of meds and variety I had been pumping in her trying to get her comfortably through the procedure.
Tuesday we had a patient who has been with us for a while come in. She is dying of liver cancer. Her granddaughter had brought her in for one last drainage of the fluid collection on her abdomen that often results from liver diseases. I was afraid she was going to die before I got her from the wheelchair to the stretcher. I asked "Tiffany" how she was able to get her to the car and then to the wheelchair to come to our department. She confessed she just hugged her and total lifted her. The patient's heart rate was in the 130s-160 and she was not making eye contact. She would answer questions slowly and laboriously. I sat down and asked Tiffany if she wanted me to transfer her grandmother to the ER or take her home to die. She decided to take her home. We sat in the hall and I held her while she cried. Tiffany is about my age and has a beautiful little boy that she takes with her everywhere she takes her grandmother. She kept her grandmother beautifully groomed with lovely hair, and manicured toes and fingers. I told Tiffany that she is one of the bravest women I've ever met. I was proud of what she had chosen to do for her grandmother. I know she'll never regret that decision to care for her grandmother. It has not been easy. But I know it was the right thing for her to do, and you could see the love they had for each other every time my patient would speak of her precious granddaughter.
Later in the day on Tuesday we had an urgent case added. The patient had an obstruction between her kidney and bladder, so her right kidney was not draining urine. Consequently this eighty something year old woman was in pain. The pain medicine had made her very confused and combative. When I got her, the doctor pointed out that the key to this procedure was going to be speed. We had to put her on her belly on a table not much wider than an ironing board and convince her to lie still while the doctor placed a tube through the skin and into the kidney to relieve the pressure. One of my fellow nurses told me, "I don't have a good feeling about this." I was surprised because while I was worried about how we were going to get her settled into position, I wasn't worried worried...Like the "not good feeling" worried.
I did express concern to the doctor that she was going septic, which simply means that there is an infection in her blood, and it goes systemic, and can have very scary results. He said "Okay, but we have to get this tube in to fix it." I agreed.
Well, after we used four staff members to wrestle a 50 kilogram woman onto the table, tied her hands and feet, and I gently medicated her, with the age and weight burdening my brain, she finally settled down. My doctor worked like a fiend and had the tube in within a five minutes.
However, her blood pressure plummeted...
She went unresponsive. We flipped her over onto the stretcher and I gave her reversals for the meds I'd given her, hoping it was a case of skinny frail white woman receiving too much sedation, even though I'd barely given her anything.
No response.
Of course her IV went bad. The good news with that was that she had beautiful veins, the kind nurses look on lustfully when they pass by you...And since she was now calm, I got a new IV in no problem. I gave her more reversals. Still no response. I started pumping her full of fluids and called in a "rapid response" which basically gets the Code Team there before a full code actually happens...
She came around a little. She began to answer questions and her pressure recovered a bit. Not enough to relax us, but a bit. We got her placed in the intensive care unit. By the time the rush was over, her son and daughter in law had went to her original room on a medical/surgical unit to get her belongings. I hated that I missed them. I had prayed with them before the procedure and reassured her daughter in law that we would take good care of her. We talked about God being in control and caring about all of our worries. We prayed that they would have peace and that the patient would be calm for the procedure. I don't know how they felt. I'm sure they were scared when they heard the call for assistance over the hospital PA. I wish I had caught up with them Wednesday to chat with them and learn how their loved one was. I wish I had sought them out at the end of the day on Tuesday to hug their necks and tell them I was sorry for their family member's illness.
But I didn't. And there wasn't even any reason not to. I was completely bored on Wednesday. So bored that a fellow nurse and I decided to do the eleven flights of stairs up and down (of course, why would we stay on the roof?) and do ten sets of squats at each landing. Then a few hours later we did it again. All I did to earn my paycheck was audit old charts and stock carts, call patients lined up for the next week, and make sure everything was neat and tidy. And while all of that needed done, it isn't what I really visualize myself doing when I head to work in the morning. I finished off my day with a four hour mandatory class. Again, not what I think of doing when I am at work.
So really there was no reason to not follow up with my little lady. I just didn't. I guess the difference with her was that whatever was wrong with her, I had no control over, yet it was a relatively expected outcome. It was all part of the pathology of her illness. I knew that, and wasn't overly surprised when events panned out like they did. Whereas the first patient had metastatic cancer, but what I was doing to her was way out of my comfort zone.
In each case I was doing what I felt was best and what I knew to do. The difference between the first and the last is back up. In the call case we were there until late in the evening, and I really didn't have a lot of people to bounce off ideas about what to do, and what else I could try to get her pain under control. The second case was during the middle of the day, and two other nurses from my department were right there talking things out with me, discussing what we should try next, and the doctor was able to get on the phone to the patient's attending physician.
So.
I'm a nurse. It's weird. Sometimes I wonder why I do it. I especially wonder what is wrong with me to love doing it. Especially as I'm sitting here typing with a headache that is directly tied to they tension I've been carrying in my neck and shoulders this week.
But I do it. I love doing it, and on some weird level I would love it if my girls did it too. We could have that weird nurse bond that commiserates about annoying, smelly patients and gripey needy doctors. We could swap horror stories of blood squirting and vomit flying...And we could commiserate over each others mistakes, and the wish we had done it different cases...
I'm a nurse.
It's what I do.
Thursday, June 9, 2011
Compassionate? Yeah. Umm. Sure.
We have a hectic day tomorrow. Since we knew our day was going to be nigh impossible tomorrow we decided to do a few cases late in the day today so we wouldn't be even crazier tomorrow.
Good planning, no?
Tom is the 6:30 am nurse. We were at our lockers changing into our "going home" shoes. Tom was digging through his disaster of a locker, because Tom is a nonrecovering hoarder. I'm grabbing my purse, emptying my pockets, and shoving a piece of Dove Special Dark Chocolate in my mouth. The following conversation went down.
Oh, by the way, our lockers are in a shared area with a men's and women's restroom on either side. Just thought you might need clarification on why I'm in a locker room with a male coworker. You should also know that Tom is infallibly polite. Our elderly patients love him because he begins every statement with "Pardon me," or "excuse me for a minute." Seriously. If you are talking to him, nearly every statement he begins starts with those two phrases. As you will see, I suffer from no such compunctions.
Moving on.
Tom: Well, Andi as of right now, I will be in tomorrow, but my ear is bothering me, and it's infected. I'm going to go home and take some medicine...(dang nurses and their self diagnosing, I don't need no stinkin' doctor attitudes)
Andi: Tom. How do you know your ear is infected?
Tom: Well, it hurts, and I feel pressure when I put my finger...
Sadly, I didn't let him finish his sentence as I know that a symptom of an ear infection is pain with manipulation of the ear.
Andi: You need to go home and take 1200mg Mucinex and some pseudoephedrine, and drink plenty of water. It's probably just congestion. You don't have an infection. (Translation: he is on call, and he better not be sick or I will have to pick it up for him.)
Tom: Well, I...(he begins to gesture towards his nose.)
Andi: Tom. Don't do your nasal rinse when you have fluid on your ears. That's bad. Take the Mucinex and Sudafed. You will be fine.
Tom: Well....Pardon me. I was going to say Afrin.
Andi: Oh. Okay. You can take Afrin. But you better take the other too. Mucinex. 1200 mg BID (twice a day to civilians). Sudafed. 30mg every four hours. You will go like this, (and I jerked my body around in a convulsive manner and made my eyes all googly) but you will be at work.
At this point my supervisor chimed in.
Julie: You will be at work on time, or possibly 3:30 am, because you won't be able to sleep taking all of the medicine Andi said to take. But she won't care, because you'll be here and yelling: Hurry up! Let's go! Get these people on the table!
Andi: That's right. And that's the most important thing. That you will be here. Tomorrow. At 6:30am.
And I slammed my locker door shut and headed to the exit...See you tomorrow Tom! Hope you feel better!
Do you think I meant that for purely selfish reasons?
Good planning, no?
Tom is the 6:30 am nurse. We were at our lockers changing into our "going home" shoes. Tom was digging through his disaster of a locker, because Tom is a nonrecovering hoarder. I'm grabbing my purse, emptying my pockets, and shoving a piece of Dove Special Dark Chocolate in my mouth. The following conversation went down.
Oh, by the way, our lockers are in a shared area with a men's and women's restroom on either side. Just thought you might need clarification on why I'm in a locker room with a male coworker. You should also know that Tom is infallibly polite. Our elderly patients love him because he begins every statement with "Pardon me," or "excuse me for a minute." Seriously. If you are talking to him, nearly every statement he begins starts with those two phrases. As you will see, I suffer from no such compunctions.
Moving on.
Tom: Well, Andi as of right now, I will be in tomorrow, but my ear is bothering me, and it's infected. I'm going to go home and take some medicine...(dang nurses and their self diagnosing, I don't need no stinkin' doctor attitudes)
Andi: Tom. How do you know your ear is infected?
Tom: Well, it hurts, and I feel pressure when I put my finger...
Sadly, I didn't let him finish his sentence as I know that a symptom of an ear infection is pain with manipulation of the ear.
Andi: You need to go home and take 1200mg Mucinex and some pseudoephedrine, and drink plenty of water. It's probably just congestion. You don't have an infection. (Translation: he is on call, and he better not be sick or I will have to pick it up for him.)
Tom: Well, I...(he begins to gesture towards his nose.)
Andi: Tom. Don't do your nasal rinse when you have fluid on your ears. That's bad. Take the Mucinex and Sudafed. You will be fine.
Tom: Well....Pardon me. I was going to say Afrin.
Andi: Oh. Okay. You can take Afrin. But you better take the other too. Mucinex. 1200 mg BID (twice a day to civilians). Sudafed. 30mg every four hours. You will go like this, (and I jerked my body around in a convulsive manner and made my eyes all googly) but you will be at work.
At this point my supervisor chimed in.
Julie: You will be at work on time, or possibly 3:30 am, because you won't be able to sleep taking all of the medicine Andi said to take. But she won't care, because you'll be here and yelling: Hurry up! Let's go! Get these people on the table!
Andi: That's right. And that's the most important thing. That you will be here. Tomorrow. At 6:30am.
And I slammed my locker door shut and headed to the exit...See you tomorrow Tom! Hope you feel better!
Do you think I meant that for purely selfish reasons?
Friday, March 25, 2011
How to Scare a Nurse
A phrase that strikes fear in a nurse's heart:
"I'm going away..."
Especially when it is accompanied by complaints of chest pain, a decreased oxygen reading, and vomiting...
Don't worry. She was fine. She had just gotten a little too sleepy from her sedatives and I had to reverse her. The reversal gave her a little asthma attack which scared her...
And me when she started telling her husband goodbye.
So, while in my head I knew (read here: was hoping and praying) it was a reaction to my reversal medication, it still scared the crap out of me.
I just thought that if you ever wanted to know how to make your nurse jump up and take notice, this could be helpful to you!
"I'm going away..."
Especially when it is accompanied by complaints of chest pain, a decreased oxygen reading, and vomiting...
Don't worry. She was fine. She had just gotten a little too sleepy from her sedatives and I had to reverse her. The reversal gave her a little asthma attack which scared her...
And me when she started telling her husband goodbye.
So, while in my head I knew (read here: was hoping and praying) it was a reaction to my reversal medication, it still scared the crap out of me.
I just thought that if you ever wanted to know how to make your nurse jump up and take notice, this could be helpful to you!
Monday, November 22, 2010
Creepiness and This Post Involves Discussion of Body Parts
Today is a day of random thoughts.
I will share them as best as I can keep up with them.
My doctor was 90 minutes late for work. When he got there, I immediately gave him a game plan, and asked about adding on more cases. I felt as if he was going to be somehow annoyed that we would be there 3 hours longer than planned, even though he was late. I felt the need to explain. Have any of you had to sit through my explanations? Let me apologize for that.
He said to no one in particular "she's not even letting me talk." I blushed and replied, "Sorry, too much caffeine with only a piece of banana bread for food. I'm jittery." Then I fear I launched into an explanation of my symptoms.
Which he didn't need.
Did you know that one time he asked me to work a patient up really quick for him, and I outright said, "No. I need food and I'm not doing one more case until I get some peanut butter in me." To say he was surprised and speechless is a slight understatement. He has since made a point to never let me get to hungry, and he makes sure everyone working with me knows, "Make sure Andi gets some food. She gets cranky when she's hungry."
One of my patients was positive for cocaine and pot. He was using a toothbrush to scratch his itchy skin.
Another patient told me I was pretty when he first saw me. I blushed, said "thanks" in a strangled laugh, uncomfortable voice and tried to move on. He stared. I asked if he was hurting, "No. My nurse on the floor gave me some ativan and pain medicine and I'm feeling pretty loose right now. But, don't worry, I won't fall asleep with a beautiful woman next to me."
And he stared.
And I got hot and sweaty and blushed and ran off.
Did I say he was only 44?
Please, by all that is good and holy, any men that are reading this, never comment on a nurse's appearance until you are well into your 70s. At that age we will smile and flirt back, but until then it's just creepy.
When I had to assist the PA to drain fluid off of his abdomen, I refused to make eye contact with him, but instead chose to look at his swallowed 2 watermelons belly...But he still stared.
Oh. And he wasn't wearing a shirt.
*Ick*
Attention all men: If you are around me, I need you to wear a shirt. Because, really where am I supposed to look?
I don't let Studmuffin work in the yard without a shirt.
You realize the shirt thing only applies to public? I walked into a patient's room to take him to our department the other day, and he was stark naked except for a small towel draped like a loin cloth. He was burning up with fever, and he was miserable. "I bet you're going to make me put on clothes to go with you," he said as his wife applied a fresh cold cloth to his neck and forehead.
"Nope! But, you do have to cover up with a sheet. I'd hate to shock anyone going down the hall."
He didn't embarrass me or make me uncomfortable at all.
I have been compiling my Christmas list. Yep. I actually have one for myself! Popcorn informed me I was being selfish like she was last year.
Just a heads up: K Cups are on the list. As is an ereader, so any Amazon gift cards would be appreciated.
Speaking of body parts: One time a certain someone told me they were glad they had small breasts, as they wouldn't ever sag. I hate to tell all of you small breasted women, but whether they are big or little, when you reach a certain age, you will find yourself picking them up to put them in your bra cup. It's just a matter of whether you have to roll them up or simply scoop and place.
Just an observation I've made.
A question that I often ponder as I observe patient lives is this: When do women change to the little black shoe with the thin little lace as their only pair of shoes? Why does this happen?
Also, I need all women to pay attention and let me know what age the hair on your legs stop growing. I'm ready to begin the countdown, so please tell me double quick when you hit that milestone.
I fear it is about the same time the hair on your chin needs shaved.
So. Who knew my random thoughts were going to be all about body parts?
Certainly not me!
My brain is a scary place to be.
Now, before I can over think this and add more random gibberish, I will sign off.
I will share them as best as I can keep up with them.
My doctor was 90 minutes late for work. When he got there, I immediately gave him a game plan, and asked about adding on more cases. I felt as if he was going to be somehow annoyed that we would be there 3 hours longer than planned, even though he was late. I felt the need to explain. Have any of you had to sit through my explanations? Let me apologize for that.
He said to no one in particular "she's not even letting me talk." I blushed and replied, "Sorry, too much caffeine with only a piece of banana bread for food. I'm jittery." Then I fear I launched into an explanation of my symptoms.
Which he didn't need.
Did you know that one time he asked me to work a patient up really quick for him, and I outright said, "No. I need food and I'm not doing one more case until I get some peanut butter in me." To say he was surprised and speechless is a slight understatement. He has since made a point to never let me get to hungry, and he makes sure everyone working with me knows, "Make sure Andi gets some food. She gets cranky when she's hungry."
One of my patients was positive for cocaine and pot. He was using a toothbrush to scratch his itchy skin.
Another patient told me I was pretty when he first saw me. I blushed, said "thanks" in a strangled laugh, uncomfortable voice and tried to move on. He stared. I asked if he was hurting, "No. My nurse on the floor gave me some ativan and pain medicine and I'm feeling pretty loose right now. But, don't worry, I won't fall asleep with a beautiful woman next to me."
And he stared.
And I got hot and sweaty and blushed and ran off.
Did I say he was only 44?
Please, by all that is good and holy, any men that are reading this, never comment on a nurse's appearance until you are well into your 70s. At that age we will smile and flirt back, but until then it's just creepy.
When I had to assist the PA to drain fluid off of his abdomen, I refused to make eye contact with him, but instead chose to look at his swallowed 2 watermelons belly...But he still stared.
Oh. And he wasn't wearing a shirt.
*Ick*
Attention all men: If you are around me, I need you to wear a shirt. Because, really where am I supposed to look?
I don't let Studmuffin work in the yard without a shirt.
You realize the shirt thing only applies to public? I walked into a patient's room to take him to our department the other day, and he was stark naked except for a small towel draped like a loin cloth. He was burning up with fever, and he was miserable. "I bet you're going to make me put on clothes to go with you," he said as his wife applied a fresh cold cloth to his neck and forehead.
"Nope! But, you do have to cover up with a sheet. I'd hate to shock anyone going down the hall."
He didn't embarrass me or make me uncomfortable at all.
I have been compiling my Christmas list. Yep. I actually have one for myself! Popcorn informed me I was being selfish like she was last year.
Just a heads up: K Cups are on the list. As is an ereader, so any Amazon gift cards would be appreciated.
Speaking of body parts: One time a certain someone told me they were glad they had small breasts, as they wouldn't ever sag. I hate to tell all of you small breasted women, but whether they are big or little, when you reach a certain age, you will find yourself picking them up to put them in your bra cup. It's just a matter of whether you have to roll them up or simply scoop and place.
Just an observation I've made.
A question that I often ponder as I observe patient lives is this: When do women change to the little black shoe with the thin little lace as their only pair of shoes? Why does this happen?
Also, I need all women to pay attention and let me know what age the hair on your legs stop growing. I'm ready to begin the countdown, so please tell me double quick when you hit that milestone.
I fear it is about the same time the hair on your chin needs shaved.
So. Who knew my random thoughts were going to be all about body parts?
Certainly not me!
My brain is a scary place to be.
Now, before I can over think this and add more random gibberish, I will sign off.
Monday, April 26, 2010
What has happened
to this world? I just went an entire week without posting. An entire week people.
What's more, this is the first time I've turned on my computer since last Thursday.
Shocking, I know.
So, here I sit racking my brain to share all of the wonders of my world, but my brain is tired, and Popcorn is watching "Spirit, Stallion of the Cimarron" while Bookworm is at softball, so I keep getting distracted...And the only things I can think to tell you are things you don't want to know.
Like, one of my coworkers happens to work recovery at another hospital. She took care of a man last week who rapped a metal ring around all of his parts and had to have surgery to cut it off.
The ring, not his parts.
Unfortunately, after driving to a free clinic which promptly said that was not a free clinic sort of deal, he had stopped and grabbed a steak sandwich and onion rings....I guess onion rings help with the inflammation.
Anyhoo, by the time he got into surgery his dangly parts were bigger than grapefruits, and they were unsure if his dumbstick would ever function properly again. Seriously, how does one get a metal ring around their parts? Why would they do it? What pleasure is there in that?
Please. I beg you not to answer that question. It is truly rhetorical.
Thank you.
Oh, WAIT! I forgot to mention that he was in such pain when he got to the ER that the nurse gave him pain medicine, then he couldn't sign his consent legally, so they had to call his son and get phone consent!
Wow! I can't even imagine how that conversation went. "Mr. So-and-so, I'm calling regarding your father. He needs emergency surgery to get a metal ring off of his you-know-whats because he's a complete wack job!"
At least, that's how I would have approached it...Y'know, since I'm such a fan of anatomically correct references to body parts and all that.
See what I mean by the only things I can think to tell about, you REALLY don't want to know.
Because, this conversation lead to all sorts of weird revelations about things we've seen, the rest of which I will spare you...
Well, now I'm off to read all of your wonderful blogs, fellow bloggers, but please do not feel offended if I fail to comment. Again, my brain is tired. And I'm in a rush. My in-laws are coming to stay tonight, and I need to clean my floors.
However, considering there's a mouse in my kitchen, somewhere, eluding my mouse traps, I'm not sure how relevant clean floors are.
But, alas Dancing With the Stars will be on soon, so I better get moving so I can watch it while I clean.
Oh, and of course though I will fail to comment on your lovely blogs, please feel obligated to comment on mine. I need to know that you are still aware of my existence after failing to post for so long. Thank you for your cooperation.
What's more, this is the first time I've turned on my computer since last Thursday.
Shocking, I know.
So, here I sit racking my brain to share all of the wonders of my world, but my brain is tired, and Popcorn is watching "Spirit, Stallion of the Cimarron" while Bookworm is at softball, so I keep getting distracted...And the only things I can think to tell you are things you don't want to know.
Like, one of my coworkers happens to work recovery at another hospital. She took care of a man last week who rapped a metal ring around all of his parts and had to have surgery to cut it off.
The ring, not his parts.
Unfortunately, after driving to a free clinic which promptly said that was not a free clinic sort of deal, he had stopped and grabbed a steak sandwich and onion rings....I guess onion rings help with the inflammation.
Anyhoo, by the time he got into surgery his dangly parts were bigger than grapefruits, and they were unsure if his dumbstick would ever function properly again. Seriously, how does one get a metal ring around their parts? Why would they do it? What pleasure is there in that?
Please. I beg you not to answer that question. It is truly rhetorical.
Thank you.
Oh, WAIT! I forgot to mention that he was in such pain when he got to the ER that the nurse gave him pain medicine, then he couldn't sign his consent legally, so they had to call his son and get phone consent!
Wow! I can't even imagine how that conversation went. "Mr. So-and-so, I'm calling regarding your father. He needs emergency surgery to get a metal ring off of his you-know-whats because he's a complete wack job!"
At least, that's how I would have approached it...Y'know, since I'm such a fan of anatomically correct references to body parts and all that.
See what I mean by the only things I can think to tell about, you REALLY don't want to know.
Because, this conversation lead to all sorts of weird revelations about things we've seen, the rest of which I will spare you...
Well, now I'm off to read all of your wonderful blogs, fellow bloggers, but please do not feel offended if I fail to comment. Again, my brain is tired. And I'm in a rush. My in-laws are coming to stay tonight, and I need to clean my floors.
However, considering there's a mouse in my kitchen, somewhere, eluding my mouse traps, I'm not sure how relevant clean floors are.
But, alas Dancing With the Stars will be on soon, so I better get moving so I can watch it while I clean.
Oh, and of course though I will fail to comment on your lovely blogs, please feel obligated to comment on mine. I need to know that you are still aware of my existence after failing to post for so long. Thank you for your cooperation.
Wednesday, April 7, 2010
Nobody Better Lay a Finger on My Baby Ruth
I have a pregnancy psychosis story for you today...
Aren't you just so thrilled you could puke?
Well, maybe not. But when I was pregnant, that's what I did.
Puke.
Puke.
Puke.
The official diagnosis is hyperemises gravidum. It basically means that you are pregnant, and yes you will puke, but take that typical little morning sickness nuisance and magnify it ten thousand times.
And, no, this is not a dramatic statement from a dramatic person...
I threw up around the clock. I would even wake up in the middle of the night sick. Pitiful. I know.
I continued to work through the entire pregnancy. Hospitalized for a few days to get some fluids pumped in me? No problem! I returned to work two days after being released...After all, I needed to save up my PTO for when the baby actually came!
So. I would puke at work of course. Seriously, I'd be taking care of a patient, get that watery mouth feeling, say excuse me, then clutching my stethoscope sprint down the hall to the bathroom...Unless of course i was unable to make it that far, in which case I would say, "Excuse me," step into the PATIENT'S bathroom and hurl... Don't you wish you could have been my patient in those days?
By the way, I didn't mention that there were 3 other ladies pregnant at the same time on the cardiac floor that I was working, and we all worked day shift. This meant that the odds were at least 2 pregnant ladies were at work on any given day. Also, please note that the fact that I spent a lot of time puking was not a secret. I worked in a hospital with about 200 beds, so everyone knew everyone, and everyone knew that our telemetry and stepdown department had a plethora of pregnant ladies....
Now, to get on with my story.
I drank fountain Dr. Pepper when I was pregnant. As a matter of fact, I had not had caffeine in four years until I was pregnant, but I craved DP, and the fountain version soothed my stomach, so I had at least one a day...
I had been working on my charting at the nurse's station. Picture my lab coat, charts, pencil, stethoscope, drink and a snack size Baby Ruth sitting in front of the computer I was working on. A patient called for assistance, so I went to see what they needed.
As I was returning to the desk, I heard my friend and also pregnant coworker say, "Dr. K, where did you get that Baby Ruth?"
"It was just sitting here."
"I think it was Andrea's..."
Okay, at this point I'm rounding the corner, and the sight that met my eyes sent me into a psychotic break of epic proportions...
Me: Are you EATING my Baby Ruth?
Dr. K, looking slightly confused, and maybe a trifle concerned: I didn't' know it was yours! It was just sitting here...
A brief background on Dr. K. He was in his internship, which means he is in his first year out of medical school... Which also means that he better be dang nice to the nurses because most of us have more real life clinical experience than him, so odds are when things start to go south, they will know more than him about how to act quickly. In addition to this you need to realize that he was famous for stealing our chairs. The second somebody got up to do whatever, he immediately plopped his carcass in their chair...
Remember we had FOUR pregnant women? This did not please us. We were cranky. We were hormonal. Our feet were swollen, and we were still working 12 hour shifts in addition to lifting patients around all day, and moving beds, and cleaning up adult body fluids...We felt we deserved a chair when we got a chance to sit down and do charting.
Return to conversation:
Me: Do you see my stethoscope? Did you notice the lab coat on the back of the chair? My charts? My DOCTOR PEPPER! How could you not think the Baby Ruth might be "somebody's" Baby Ruth? What is wrong with you?! Oh, and by the way, this happens to be the NURSES station, not the doctors station! You are barely out of school and you think you have the right to just come in here and take our chairs every time we stand up! You are the WORST!!!
Dr. K, beginning to look very afraid: I'm sorry, I didn't know it belonged to anyone...
Oh, and Gentle Reader, did you know he also happened to be the proud papa of four kids? You'd think he'd have a better handling of pregnant women than just "I didn't know it belonged to anyone," which was the only defense he could think of...And yes, I really did say all of that, and probably more. I was BRUTAL.
Of course, I felt bad once the initial surge of rage passed. I apologized. I even did it in front of everyone, so he could see I really meant it. I was truly ashamed of my outburst.
Apparently, he was ashamed of his actions too. The next day he brought me a king size Baby Ruth, when he had only eaten a snack size. I felt really small when he did that.
Oh, but you should also know that he went on to his surgical residency in our hospital.
And, sure enough, he turned out to be one of the most arrogant doctors we had.
And, yes. He continued to steal our chairs the minute we stood up.
But, I doubt he ever picked up a random candy bar sitting at the desk without first checking if it belonged to anyone!
Aren't you just so thrilled you could puke?
Well, maybe not. But when I was pregnant, that's what I did.
Puke.
Puke.
Puke.
The official diagnosis is hyperemises gravidum. It basically means that you are pregnant, and yes you will puke, but take that typical little morning sickness nuisance and magnify it ten thousand times.
And, no, this is not a dramatic statement from a dramatic person...
I threw up around the clock. I would even wake up in the middle of the night sick. Pitiful. I know.
I continued to work through the entire pregnancy. Hospitalized for a few days to get some fluids pumped in me? No problem! I returned to work two days after being released...After all, I needed to save up my PTO for when the baby actually came!
So. I would puke at work of course. Seriously, I'd be taking care of a patient, get that watery mouth feeling, say excuse me, then clutching my stethoscope sprint down the hall to the bathroom...Unless of course i was unable to make it that far, in which case I would say, "Excuse me," step into the PATIENT'S bathroom and hurl... Don't you wish you could have been my patient in those days?
By the way, I didn't mention that there were 3 other ladies pregnant at the same time on the cardiac floor that I was working, and we all worked day shift. This meant that the odds were at least 2 pregnant ladies were at work on any given day. Also, please note that the fact that I spent a lot of time puking was not a secret. I worked in a hospital with about 200 beds, so everyone knew everyone, and everyone knew that our telemetry and stepdown department had a plethora of pregnant ladies....
Now, to get on with my story.
I drank fountain Dr. Pepper when I was pregnant. As a matter of fact, I had not had caffeine in four years until I was pregnant, but I craved DP, and the fountain version soothed my stomach, so I had at least one a day...
I had been working on my charting at the nurse's station. Picture my lab coat, charts, pencil, stethoscope, drink and a snack size Baby Ruth sitting in front of the computer I was working on. A patient called for assistance, so I went to see what they needed.
As I was returning to the desk, I heard my friend and also pregnant coworker say, "Dr. K, where did you get that Baby Ruth?"
"It was just sitting here."
"I think it was Andrea's..."
Okay, at this point I'm rounding the corner, and the sight that met my eyes sent me into a psychotic break of epic proportions...
Me: Are you EATING my Baby Ruth?
Dr. K, looking slightly confused, and maybe a trifle concerned: I didn't' know it was yours! It was just sitting here...
A brief background on Dr. K. He was in his internship, which means he is in his first year out of medical school... Which also means that he better be dang nice to the nurses because most of us have more real life clinical experience than him, so odds are when things start to go south, they will know more than him about how to act quickly. In addition to this you need to realize that he was famous for stealing our chairs. The second somebody got up to do whatever, he immediately plopped his carcass in their chair...
Remember we had FOUR pregnant women? This did not please us. We were cranky. We were hormonal. Our feet were swollen, and we were still working 12 hour shifts in addition to lifting patients around all day, and moving beds, and cleaning up adult body fluids...We felt we deserved a chair when we got a chance to sit down and do charting.
Return to conversation:
Me: Do you see my stethoscope? Did you notice the lab coat on the back of the chair? My charts? My DOCTOR PEPPER! How could you not think the Baby Ruth might be "somebody's" Baby Ruth? What is wrong with you?! Oh, and by the way, this happens to be the NURSES station, not the doctors station! You are barely out of school and you think you have the right to just come in here and take our chairs every time we stand up! You are the WORST!!!
Dr. K, beginning to look very afraid: I'm sorry, I didn't know it belonged to anyone...
Oh, and Gentle Reader, did you know he also happened to be the proud papa of four kids? You'd think he'd have a better handling of pregnant women than just "I didn't know it belonged to anyone," which was the only defense he could think of...And yes, I really did say all of that, and probably more. I was BRUTAL.
Of course, I felt bad once the initial surge of rage passed. I apologized. I even did it in front of everyone, so he could see I really meant it. I was truly ashamed of my outburst.
Apparently, he was ashamed of his actions too. The next day he brought me a king size Baby Ruth, when he had only eaten a snack size. I felt really small when he did that.
Oh, but you should also know that he went on to his surgical residency in our hospital.
And, sure enough, he turned out to be one of the most arrogant doctors we had.
And, yes. He continued to steal our chairs the minute we stood up.
But, I doubt he ever picked up a random candy bar sitting at the desk without first checking if it belonged to anyone!
Thursday, February 25, 2010
Channeling her uterus...
Do you know why you have a uterus?
Well of course, there's the whole child bearing thing. We'll call that the no-brainer use. However, that is a relatively short lived use of it if you're covering the whole life span. Which, of course, I always include the entire life span...
First of all, you should know that your uterus is integral in locating things.
Surely you've noticed this? Studmuffin and I used to joke about him "looking everywhere" for something and still being unable to find it. Of course, I think part of the problem with men being unable to locate things comes from their method of searching. It involves standing. And turning around in a circle. When that technique fails, they throw in one last ditch effort to find the elusive item: They hold their hands up in the air, palms open, and wait for it to fall from the sky. When this does not reveal the location of the missing item, they are at complete loss of where to find it.
The reality is, that we as women have an unfair advantage in locating missing items over men. God gave us a uterus. Yep, you may be unaware of it, but when you are finding that missing set of keys, or the lost tennis shoe, or even the scarf that has to be worn with the hat that goes with the mittens, because they are all turquoise and you simply canNOT wear a brown hat with this ensemble....You are channeling your uterus. Thankfully, we don't have to consciously seek out the connection. It is just there. And it is beautiful.
The second little know purpose of your uterus is multi-tasking. We all know that women are better at multi-tasking than men. We have all just taken it for granted all these years that women know, without being told, that it is possible to run the dishwasher, washing machine, and even run the vacuum at the same time. Revolutionary!
Here's a little aside for you, Gentle Reader: I made a slip up the other day at work. Nothing big. Nothing patient related. But, it was a goof nonetheless. I was explaining what happened, and it was mentioned that I was talking while in the middle of writing the note. One of my (male) coworkers said, "OH! You were talking. You were trying to do too many things at once." Then we all died laughing. Because, seriously. Anyone who spends 30 seconds with me understands that talking does not interfere with any task I'm doing. Otherwise I would never get anything done! That is a sad, true statement....
The third use for your uterus is one of the most mysterious, and yet most cherished qualities about us as women: It allows us to change our minds. Not only can we change our minds, but we can do it whenever we want. With no real reason or purpose. The mind is changed. There is no unchanging the mind once it is changed. Unless of course the uterus deems it. Then, of course, the mind will promptly be reverted to it's original plan or opinion. It is truly a beautiful phenomena, Dear Reader. Just beautiful...
Well, I can hear the question forming in many of your minds as you read this revolutionary post: What about women who have had a hysterectomy? Well, there is really only one good answer to that question, Gentle Reader. We may not like the answer, but if we search our souls, you will know it to be true: They go crazy.
Yep, their whole world go kaplooey...
Okay, I'm totally kidding about that, but I will take this opportunity to give you totally unsolicited medical advice. Any men who cringe at "female" stuff should stop and run right now.
Go ahead, you can leave...We all know you don't want to hear this anyway....
Alright, now that the boys are gone, here's the thing. Many women suffer form uterine fibroids. These fibroids cause much pain and discomfort for women. Many doctors will advise you to have a hysterectomy due to the blood loss and pain you are suffering. Before you take this drastic step, please ask about uterine fibroid embolization. This is a minimally invasive procedure where a doctor goes in and cuts off blood supply to the fibroids, thereby eliminating them. Follow this link to learn more. Just hear my on this: You get to keep your uterus.
And we have already established the beauty of that...
Monday night we had a banquet to attend at church. I forgot to remind Studmuffin to put the tickets in his billfold before he left for work. I was meeting them at the church since I was coming directly from work. Well, I remembered to call him on my way home to be sure he had them...
Sure enough, he didn't. The got back in his truck and went home to grab them.
Where he couldn't find them.
Despite me saying exactly where they were.
He went in the bedroom to see if they were maybe on the dresser...
Bookworm found them and brought them to him...
They were where I had said, but of course, he was determined that she had an unfair advantage over him....
Yep.
Her uterus.
Well of course, there's the whole child bearing thing. We'll call that the no-brainer use. However, that is a relatively short lived use of it if you're covering the whole life span. Which, of course, I always include the entire life span...
First of all, you should know that your uterus is integral in locating things.
Surely you've noticed this? Studmuffin and I used to joke about him "looking everywhere" for something and still being unable to find it. Of course, I think part of the problem with men being unable to locate things comes from their method of searching. It involves standing. And turning around in a circle. When that technique fails, they throw in one last ditch effort to find the elusive item: They hold their hands up in the air, palms open, and wait for it to fall from the sky. When this does not reveal the location of the missing item, they are at complete loss of where to find it.
The reality is, that we as women have an unfair advantage in locating missing items over men. God gave us a uterus. Yep, you may be unaware of it, but when you are finding that missing set of keys, or the lost tennis shoe, or even the scarf that has to be worn with the hat that goes with the mittens, because they are all turquoise and you simply canNOT wear a brown hat with this ensemble....You are channeling your uterus. Thankfully, we don't have to consciously seek out the connection. It is just there. And it is beautiful.
The second little know purpose of your uterus is multi-tasking. We all know that women are better at multi-tasking than men. We have all just taken it for granted all these years that women know, without being told, that it is possible to run the dishwasher, washing machine, and even run the vacuum at the same time. Revolutionary!
Here's a little aside for you, Gentle Reader: I made a slip up the other day at work. Nothing big. Nothing patient related. But, it was a goof nonetheless. I was explaining what happened, and it was mentioned that I was talking while in the middle of writing the note. One of my (male) coworkers said, "OH! You were talking. You were trying to do too many things at once." Then we all died laughing. Because, seriously. Anyone who spends 30 seconds with me understands that talking does not interfere with any task I'm doing. Otherwise I would never get anything done! That is a sad, true statement....
The third use for your uterus is one of the most mysterious, and yet most cherished qualities about us as women: It allows us to change our minds. Not only can we change our minds, but we can do it whenever we want. With no real reason or purpose. The mind is changed. There is no unchanging the mind once it is changed. Unless of course the uterus deems it. Then, of course, the mind will promptly be reverted to it's original plan or opinion. It is truly a beautiful phenomena, Dear Reader. Just beautiful...
Well, I can hear the question forming in many of your minds as you read this revolutionary post: What about women who have had a hysterectomy? Well, there is really only one good answer to that question, Gentle Reader. We may not like the answer, but if we search our souls, you will know it to be true: They go crazy.
Yep, their whole world go kaplooey...
Okay, I'm totally kidding about that, but I will take this opportunity to give you totally unsolicited medical advice. Any men who cringe at "female" stuff should stop and run right now.
Go ahead, you can leave...We all know you don't want to hear this anyway....
Alright, now that the boys are gone, here's the thing. Many women suffer form uterine fibroids. These fibroids cause much pain and discomfort for women. Many doctors will advise you to have a hysterectomy due to the blood loss and pain you are suffering. Before you take this drastic step, please ask about uterine fibroid embolization. This is a minimally invasive procedure where a doctor goes in and cuts off blood supply to the fibroids, thereby eliminating them. Follow this link to learn more. Just hear my on this: You get to keep your uterus.
And we have already established the beauty of that...
Monday night we had a banquet to attend at church. I forgot to remind Studmuffin to put the tickets in his billfold before he left for work. I was meeting them at the church since I was coming directly from work. Well, I remembered to call him on my way home to be sure he had them...
Sure enough, he didn't. The got back in his truck and went home to grab them.
Where he couldn't find them.
Despite me saying exactly where they were.
He went in the bedroom to see if they were maybe on the dresser...
Bookworm found them and brought them to him...
They were where I had said, but of course, he was determined that she had an unfair advantage over him....
Yep.
Her uterus.
Nursing Stuff
Today Bookworm woke up about 5:30. With a stomach bug...
About her 4th trip to the bathroom, she pointed out to me that "IT'S HURTING WORSE EVERY TIME!!!" I kind of got the idea that she felt like I could fix it. Especially when she was lying on the bathroom floor, curled in the fetal position, shaking, pale, and moaning...
Do you remember that when you were a kid? I can remember thinking that surely my mom should be able to do SOMETHING for this malady...Other than walk around spraying Lysol continuously....I gotta confess: That was exactly what I was doing, because I was showering in the hall bath when she first woke up, so her first visit was to my bathroom. Then, she came to tell me she was sick in HER bathroom, then had another episode. So, I was disinfecting my bathroom, and I ordered her to stay put unless it was to go her bed, directly to her bed, do not cross go, do not touch anything, and do not share your cooties with anyone else!
Aren't you glad your mom isn't a nurse?
Speaking of nursing, Studmuffin and I tag teamed staying home with the sickling today. He took the morning shift, then I came home about one o'clock for him to get some stuff done at work. Since I work in a procedural area, we tend to stack our mornings heavy, so if I'm going to miss part of the day, afternoons are lightest. At least, that's what we shoot for. Otherwise, we may be there late recovering patients from sedation...
Anyway, I had a frequent flyer patient today. I'll call her Miss X. Miss X comes to us AT LEAST once a month. She originally came for us to repair her dialysis fistula...There are people who have dialysis grafts that work for years and years. Then, you have the Miss X's of the world who have endless problems with them. Then, she got a kidney transplant, and we saw her to do a follow up biopsy of her transplanted kidney. Then it got an abscess. Then she had some liver failure...I keep telling her we don't give advantage miles, but she continues to come.
She is a sweet lady. She is single, but has a boyfriend who takes care of her. I've never seen any other family with her...
Today she needed some fluid drained from around her lungs, and she had a "collection of fluid surrounding her spleen" that we needed to use our CT to guide the doctor in placing the tube for drainage...
I had just finished my previous procedure (did I mention we were down 2 nurses today?) and returned him to the holding area, when my coworker handed me Miss X. She gave me a brief report, and we were off. She looked bad. Really bad....I got that weird, "this is not going to go well" feeling in my stomach that I've learned to never ignore.
I took her in, placed her on our table, hooked her up to the monitor...
Whoa! Her oxygen was only 84%. No problem, I'll bump her up...
And, alrighty, I will bump her up some more...
Okay. Her heart rate is increasing. She is now sitting at about 140. She started out around 115...
Let's try a mask. The doctor is on the phone, discussing his next case with the attending for that patient...I interrupted and voiced my concerns for her. I want him to drain her lung before we attempt the spleen, which is exact opposite of our plan. He wants to tap that fluid around her spleen, then have the PA take care of that lung. If there is fluid around her lung, that is inhibiting her breathing. I can hear her rattling from across the room....
I have the radiology tech help me put her back on the stretcher, as Miss X is now telling me the only way she can breathe is sitting up in a tripod position (leaning forward, weight on elbows) and feet dangling. She has so much fluid overload that even her feet up on the bed are placing an excess burden of fluid around her lungs...We sit her accordingly...
I have now moved her to what we call a nonrebreather. This is the maximum amount of oxygen I can give a patient, barring a c-pap, or bipap, or worse, a ventilator all of which involve machines to help push her lungs open. Her heart rate remains elevated. I see that she has received some lasix in her IV this morning, and I can tell by her catheter that she is pouring urine out. Good sign for this fluid I can hear her trying to breathe around, but not working quickly enough...
We had to cancel our procedure. I gotta say, I breathed a hallelujah. I have a relationship with Miss X. She and I had prayed when she first started spiraling down. She told me, "Thank you for praying, Andi. I know God is in control of all things."
Wow.
My eyes are tearing, just as they were as I frantically called her doctor, EKG, respiratory, bed assignments to request an ICU bed for her, and nagged my doctor to do something...
The peace her statement invokes. I know God is in control. I know He orchestrated who would be with her, and who would be in that room with me. I know He was in the room....Thank God I have such a great team, who is willing to jump in and help when they see a need. Everyone was there and ready to take action.
I eventually got orders to transfer her to the unit. I haggled with the doctor, because there were no immediate ICU beds (the ICUs have to keep one bed open for codes), and I needed orders NOW...
There is nothing worse than feeling like you are doing NOTHING when you see your patient declining, and you need to feel like you are doing SOMETHING...
Dr. T said, "Get her to the unit, that is your order."
So, I told her I was ordering an EKG...
Dr. F, her pulmonologist said, "get her to the unit, that is your order."
I nagged and eventually got an order for a stat chest xray and blood gases...
Dr. S told me "She needs the ICU. Then her doctors will write orders."
One doctor gave an order for more lasix to pull off some of the massive amount of fluids that were filling in her lungs...
I did get her to the unit.
Alive.
I gotta say, I was worried that was NOT going to be the situation for a while. I was begging for lopressor, a medication that decreases heart rate and blood pressure. At one point her pressure was 250/120...
I asked for adenosine...
Adenosine is this really cool drug that has a nano-second half life. You have to give it super fast, or it won't work...It stops the heart for just a second, and then the heart restarts. Since the half-life is so fast, it's literally just a little pause...And then, the hope is, the patient's new rhythm will be normal...
I didn't really expect them to give me the adenosine because it would not have treated her particular cause for the rapid heart rate...
You know I have dime store diagnosis, right? I think she was going septic. She had a nonexistent white blood count. She had a fever of 102. With the anti-rejection drugs she takes for her kidneys, I think her body was unable to fight off whatever was attacking her...
Here's the cycle I was desperate to stop: Temperature climbs, heart rate sky rockets, and eventually, the blood pressure tanks. To, like nonexistent tanks...
But, thankfully, God gave her a bed in the ICU before the cycle continued...
I don't know what happened to her after I turned her over to the ICU nurse. I had to come home for my sick kid. But, I work tomorrow, and I will definitely be checking on Miss X.
Do you want to know the really weird/sick thing about this whole ordeal?
I left work thinking, "I love being a nurse. WHY do I love this job? There is something seriously wrong with me to willingly do this..."
Now, I think most of you find that entire story confusing and boring. But, it's what I do. It's what I love. So, at times you will have to read about it... It purges me and helps me think about what I could have done better. Maybe I should have called a "rapid response." That would have sped things up. I should have called this, because this team is designed to help the decision process and move things along quickly...Anyway, I'm stopping now.
On a lighter note:
Studmuffin: Popcorn, why did you make a 73 on this paper? You said you're the smartest kid in class?
Popcorn: Dad, I'm not perfect!
Studmuffin: I would say not. This is 27 points away from perfect...Which would be a lot closer if you had actually finished your paper!
Popcorn: Well, I can't do everything right!
Glad to hear she's not overly burdened with that situation!
About her 4th trip to the bathroom, she pointed out to me that "IT'S HURTING WORSE EVERY TIME!!!" I kind of got the idea that she felt like I could fix it. Especially when she was lying on the bathroom floor, curled in the fetal position, shaking, pale, and moaning...
Do you remember that when you were a kid? I can remember thinking that surely my mom should be able to do SOMETHING for this malady...Other than walk around spraying Lysol continuously....I gotta confess: That was exactly what I was doing, because I was showering in the hall bath when she first woke up, so her first visit was to my bathroom. Then, she came to tell me she was sick in HER bathroom, then had another episode. So, I was disinfecting my bathroom, and I ordered her to stay put unless it was to go her bed, directly to her bed, do not cross go, do not touch anything, and do not share your cooties with anyone else!
Aren't you glad your mom isn't a nurse?
Speaking of nursing, Studmuffin and I tag teamed staying home with the sickling today. He took the morning shift, then I came home about one o'clock for him to get some stuff done at work. Since I work in a procedural area, we tend to stack our mornings heavy, so if I'm going to miss part of the day, afternoons are lightest. At least, that's what we shoot for. Otherwise, we may be there late recovering patients from sedation...
Anyway, I had a frequent flyer patient today. I'll call her Miss X. Miss X comes to us AT LEAST once a month. She originally came for us to repair her dialysis fistula...There are people who have dialysis grafts that work for years and years. Then, you have the Miss X's of the world who have endless problems with them. Then, she got a kidney transplant, and we saw her to do a follow up biopsy of her transplanted kidney. Then it got an abscess. Then she had some liver failure...I keep telling her we don't give advantage miles, but she continues to come.
She is a sweet lady. She is single, but has a boyfriend who takes care of her. I've never seen any other family with her...
Today she needed some fluid drained from around her lungs, and she had a "collection of fluid surrounding her spleen" that we needed to use our CT to guide the doctor in placing the tube for drainage...
I had just finished my previous procedure (did I mention we were down 2 nurses today?) and returned him to the holding area, when my coworker handed me Miss X. She gave me a brief report, and we were off. She looked bad. Really bad....I got that weird, "this is not going to go well" feeling in my stomach that I've learned to never ignore.
I took her in, placed her on our table, hooked her up to the monitor...
Whoa! Her oxygen was only 84%. No problem, I'll bump her up...
And, alrighty, I will bump her up some more...
Okay. Her heart rate is increasing. She is now sitting at about 140. She started out around 115...
Let's try a mask. The doctor is on the phone, discussing his next case with the attending for that patient...I interrupted and voiced my concerns for her. I want him to drain her lung before we attempt the spleen, which is exact opposite of our plan. He wants to tap that fluid around her spleen, then have the PA take care of that lung. If there is fluid around her lung, that is inhibiting her breathing. I can hear her rattling from across the room....
I have the radiology tech help me put her back on the stretcher, as Miss X is now telling me the only way she can breathe is sitting up in a tripod position (leaning forward, weight on elbows) and feet dangling. She has so much fluid overload that even her feet up on the bed are placing an excess burden of fluid around her lungs...We sit her accordingly...
I have now moved her to what we call a nonrebreather. This is the maximum amount of oxygen I can give a patient, barring a c-pap, or bipap, or worse, a ventilator all of which involve machines to help push her lungs open. Her heart rate remains elevated. I see that she has received some lasix in her IV this morning, and I can tell by her catheter that she is pouring urine out. Good sign for this fluid I can hear her trying to breathe around, but not working quickly enough...
We had to cancel our procedure. I gotta say, I breathed a hallelujah. I have a relationship with Miss X. She and I had prayed when she first started spiraling down. She told me, "Thank you for praying, Andi. I know God is in control of all things."
Wow.
My eyes are tearing, just as they were as I frantically called her doctor, EKG, respiratory, bed assignments to request an ICU bed for her, and nagged my doctor to do something...
The peace her statement invokes. I know God is in control. I know He orchestrated who would be with her, and who would be in that room with me. I know He was in the room....Thank God I have such a great team, who is willing to jump in and help when they see a need. Everyone was there and ready to take action.
I eventually got orders to transfer her to the unit. I haggled with the doctor, because there were no immediate ICU beds (the ICUs have to keep one bed open for codes), and I needed orders NOW...
There is nothing worse than feeling like you are doing NOTHING when you see your patient declining, and you need to feel like you are doing SOMETHING...
Dr. T said, "Get her to the unit, that is your order."
So, I told her I was ordering an EKG...
Dr. F, her pulmonologist said, "get her to the unit, that is your order."
I nagged and eventually got an order for a stat chest xray and blood gases...
Dr. S told me "She needs the ICU. Then her doctors will write orders."
One doctor gave an order for more lasix to pull off some of the massive amount of fluids that were filling in her lungs...
I did get her to the unit.
Alive.
I gotta say, I was worried that was NOT going to be the situation for a while. I was begging for lopressor, a medication that decreases heart rate and blood pressure. At one point her pressure was 250/120...
I asked for adenosine...
Adenosine is this really cool drug that has a nano-second half life. You have to give it super fast, or it won't work...It stops the heart for just a second, and then the heart restarts. Since the half-life is so fast, it's literally just a little pause...And then, the hope is, the patient's new rhythm will be normal...
I didn't really expect them to give me the adenosine because it would not have treated her particular cause for the rapid heart rate...
You know I have dime store diagnosis, right? I think she was going septic. She had a nonexistent white blood count. She had a fever of 102. With the anti-rejection drugs she takes for her kidneys, I think her body was unable to fight off whatever was attacking her...
Here's the cycle I was desperate to stop: Temperature climbs, heart rate sky rockets, and eventually, the blood pressure tanks. To, like nonexistent tanks...
But, thankfully, God gave her a bed in the ICU before the cycle continued...
I don't know what happened to her after I turned her over to the ICU nurse. I had to come home for my sick kid. But, I work tomorrow, and I will definitely be checking on Miss X.
Do you want to know the really weird/sick thing about this whole ordeal?
I left work thinking, "I love being a nurse. WHY do I love this job? There is something seriously wrong with me to willingly do this..."
Now, I think most of you find that entire story confusing and boring. But, it's what I do. It's what I love. So, at times you will have to read about it... It purges me and helps me think about what I could have done better. Maybe I should have called a "rapid response." That would have sped things up. I should have called this, because this team is designed to help the decision process and move things along quickly...Anyway, I'm stopping now.
On a lighter note:
Studmuffin: Popcorn, why did you make a 73 on this paper? You said you're the smartest kid in class?
Popcorn: Dad, I'm not perfect!
Studmuffin: I would say not. This is 27 points away from perfect...Which would be a lot closer if you had actually finished your paper!
Popcorn: Well, I can't do everything right!
Glad to hear she's not overly burdened with that situation!
Tuesday, February 16, 2010
How to Perform the Heimlech Maneuver
Did you know I've actually had to rescue Popcorn from choking 4 times?
That's right, four times...
I will spare you the details of the first three, and skip to our most recent event...
The Setting: A Mexican Restaurant
The Cast of Characters:
My Father-in-law aka Tom
Mother-in-law aka Scotty
Bookworm as herself
Popcorn as herself
Studmuffin as himself
Me as, well, myself (duh)
Waitress
Manager
Restaurant is full of diners. It is a Friday night.
Seating arrangements: We are seated at a booth. Popcorn is sitting on the outside edge with Tom next to her, and Scotty on the inside. We are, obviously, seated across, with Studmuffin on the outside, then me, then Bookworm.
Opening scene: The waitress is delivering our food. Well, actually she is delivering my food, because she forgot to put in my order when she put in everyone else's and did not realize it until she had passed out all the food, and I had nuthin'...
Waitress: Here's your food ma'am. So sorry about the delay. Is there anything else I can bring you?
Studmuffin: Well, we still need those napkins. And refills for our drinks, please?
I cast my gaze across the table, seeing if there is anything else we need... I do a double take at Popcorn.
Me: Are you choking?
Popcorn: No verbal response here, she is clutching her throat, and is a scary red...
Waitress: OH MY GOSH!!! SHE IS REALLY CHOKING!!
Studmuffin is already attempting to get up, so I can help her...However, unbeknownst to me, his feet were crossed under the table, and when he went to stand, his foot got caught on the pedestal. In my mind he is S.L.O.W.L.Y. getting up. I try to gently nudge him out of the way. He continues to piddle around, so I nudged him again...Just a little nudge mind you. Certainly not a big enough nudge to result in him flying out of the booth and collapsing onto the floor. Oh, and it might be helpful, for your visual purposes to know that he still had his arm in an immobilizer...
I climbed over the top of him, and grabbed Popcorn out of the booth. I positioned her for the first abdominal thrust...
For some strange reason, when I thrust up, my feet tried to fly out from under me...
She continued to choke...
I thrust up again, and again, my feet start sliding all over the place. I can barely maintain my balance, and yet poor Popcorn's feet are flying up behind me at the same time...
Finally, after what felt like 10 minutes, but was actually only maybe 5 thrusts, it came out...
A piece of cheese enchilada. Apparently, the reason it took so much to get out was because it would start to come out after my thrust, and then she would try to gasp for air and suck it right back down!!!
I swiftly walked her to the bathroom to try and compose both her and myself. We cried. We laughed. We hugged...
We returned to the table a few minutes later, and this is the conversation that followed.
Bookworm: Mom, you should NOT have thrown Dad on the floor like that! He could have hurt his shoulder!
Me: I didn't throw him on the floor. He fell.
Studmuffin: Nope. My foot was caught and you shoved me out of the booth and onto the floor.
Me: Oh. Well, I'm sorry, but Popcorn couldn't breathe! I had to help her! (I was a tad embarrassed at the thought of throwing my one-armed husband onto the floor in a crowded restaurant.)
Studmuffin: You should have seen yourself. You were jerking Popcorn around like a rag doll, and you kept almost falling down...
Me: Yeah. What was up with that? My feet were skidding all over the place. I think this floor must need mopped. I think it's greasy or something.
Studmuffin: You knocked a glass of water off of the table when you were grabbing her. Your feet were slipping in a puddle on the floor....
So, just in case you don't get the full picture, here it was: I would do an upward thrust. My feet would fly to the side and her feet would slip behind her and end up between my legs. Kind of like those dances where the man slides the lady between his legs, only she was facing away from me. I would drag her back to standing, reposition her, do an upward thrust, and the whole process would repeat. My feet would slide our spread eagle, and her feet would fly underneath me... In addition to this, the enchilada had actually tried to come out 3 different times, but she would suck it back in when she tried to gasp for breath. I could not see this, but the question I now have is this: Why didn't anyone grab the food after that happened the first time, so she wouldn't suck it back in...
Of course, for all I know Studmuffin hadn't been able to drag himself off of the floor yet...And my in-laws were in complete shock over the spectacle I was making of myself... And the restaurant manager was standing next to the waitress, huddled in the corner behind me. Watching the entire scene in horror...But again, this is all in my peripheral vision, and my perceptions are clouded by the sheer adrenalin that was pumping through me...
Me: So. Do you think anyone was watching us?
Studmuffin, outright laughing at me now: Babe. Seriously? All conversation and motion stopped when you started jerking our poor daughter around like a rag doll. Yes. I think it's safe to say that EVERYONE was watching.
Me: Dang................... Now. I wonder if they would heat up my food? I'm starving...
And I proceeded to eat every bite of food on my plate. And so did Popcorn. If that gal isn't a nurse in the making, I don't know what is!
That's right, four times...
I will spare you the details of the first three, and skip to our most recent event...
The Setting: A Mexican Restaurant
The Cast of Characters:
My Father-in-law aka Tom
Mother-in-law aka Scotty
Bookworm as herself
Popcorn as herself
Studmuffin as himself
Me as, well, myself (duh)
Waitress
Manager
Restaurant is full of diners. It is a Friday night.
Seating arrangements: We are seated at a booth. Popcorn is sitting on the outside edge with Tom next to her, and Scotty on the inside. We are, obviously, seated across, with Studmuffin on the outside, then me, then Bookworm.
Opening scene: The waitress is delivering our food. Well, actually she is delivering my food, because she forgot to put in my order when she put in everyone else's and did not realize it until she had passed out all the food, and I had nuthin'...
Waitress: Here's your food ma'am. So sorry about the delay. Is there anything else I can bring you?
Studmuffin: Well, we still need those napkins. And refills for our drinks, please?
I cast my gaze across the table, seeing if there is anything else we need... I do a double take at Popcorn.
Me: Are you choking?
Popcorn: No verbal response here, she is clutching her throat, and is a scary red...
Waitress: OH MY GOSH!!! SHE IS REALLY CHOKING!!
Studmuffin is already attempting to get up, so I can help her...However, unbeknownst to me, his feet were crossed under the table, and when he went to stand, his foot got caught on the pedestal. In my mind he is S.L.O.W.L.Y. getting up. I try to gently nudge him out of the way. He continues to piddle around, so I nudged him again...Just a little nudge mind you. Certainly not a big enough nudge to result in him flying out of the booth and collapsing onto the floor. Oh, and it might be helpful, for your visual purposes to know that he still had his arm in an immobilizer...
I climbed over the top of him, and grabbed Popcorn out of the booth. I positioned her for the first abdominal thrust...
For some strange reason, when I thrust up, my feet tried to fly out from under me...
She continued to choke...
I thrust up again, and again, my feet start sliding all over the place. I can barely maintain my balance, and yet poor Popcorn's feet are flying up behind me at the same time...
Finally, after what felt like 10 minutes, but was actually only maybe 5 thrusts, it came out...
A piece of cheese enchilada. Apparently, the reason it took so much to get out was because it would start to come out after my thrust, and then she would try to gasp for air and suck it right back down!!!
I swiftly walked her to the bathroom to try and compose both her and myself. We cried. We laughed. We hugged...
We returned to the table a few minutes later, and this is the conversation that followed.
Bookworm: Mom, you should NOT have thrown Dad on the floor like that! He could have hurt his shoulder!
Me: I didn't throw him on the floor. He fell.
Studmuffin: Nope. My foot was caught and you shoved me out of the booth and onto the floor.
Me: Oh. Well, I'm sorry, but Popcorn couldn't breathe! I had to help her! (I was a tad embarrassed at the thought of throwing my one-armed husband onto the floor in a crowded restaurant.)
Studmuffin: You should have seen yourself. You were jerking Popcorn around like a rag doll, and you kept almost falling down...
Me: Yeah. What was up with that? My feet were skidding all over the place. I think this floor must need mopped. I think it's greasy or something.
Studmuffin: You knocked a glass of water off of the table when you were grabbing her. Your feet were slipping in a puddle on the floor....
So, just in case you don't get the full picture, here it was: I would do an upward thrust. My feet would fly to the side and her feet would slip behind her and end up between my legs. Kind of like those dances where the man slides the lady between his legs, only she was facing away from me. I would drag her back to standing, reposition her, do an upward thrust, and the whole process would repeat. My feet would slide our spread eagle, and her feet would fly underneath me... In addition to this, the enchilada had actually tried to come out 3 different times, but she would suck it back in when she tried to gasp for breath. I could not see this, but the question I now have is this: Why didn't anyone grab the food after that happened the first time, so she wouldn't suck it back in...
Of course, for all I know Studmuffin hadn't been able to drag himself off of the floor yet...And my in-laws were in complete shock over the spectacle I was making of myself... And the restaurant manager was standing next to the waitress, huddled in the corner behind me. Watching the entire scene in horror...But again, this is all in my peripheral vision, and my perceptions are clouded by the sheer adrenalin that was pumping through me...
Me: So. Do you think anyone was watching us?
Studmuffin, outright laughing at me now: Babe. Seriously? All conversation and motion stopped when you started jerking our poor daughter around like a rag doll. Yes. I think it's safe to say that EVERYONE was watching.
Me: Dang................... Now. I wonder if they would heat up my food? I'm starving...
And I proceeded to eat every bite of food on my plate. And so did Popcorn. If that gal isn't a nurse in the making, I don't know what is!
Subscribe to:
Posts (Atom)